Exosomal Non-Coding RNAs Orchestrate Immune-Metabolic Networks in Triple-Negative Breast Cancer
1 Institute of Precision Cancer Medicine and Pathology, School of Medicine, State Key Laboratory of Bioactive Molecules and Drugability Assessment, Jinan University, Guangzhou, China
2 Henan Key Laboratory of Cancer Epigenetics; Cancer Hospital, The First Affiliated Hospital, and College of Clinical Medicine of Henan University of Science and Technology, Luoyang, China
3 Department of Pathology, Gongli Hospital of Shanghai Pudong New Area, Shanghai, China
4 Department of Pathology, Heping Hospital, Changzhi Medical College, Changzhi, China
5 Department of Pharmacy, Red Cross Hospital, Jinan University, Guangzhou, China
6 Department of General Surgery, The First Affiliated Hospital of Jinan University, Guangzhou, China
7 Department of Breast Surgery, Nanchang People’s Hospital, Nanchang, China
8 Department of Radiotherapy, The Third Affiliated Hospital of Kunming Medical University, Yunnan Cancer Hospital, Peking University Cancer Hospital Yunnan, Kunming, China
9 Department of Pharmacy, Red Cross Hospital, Jinan University, MOE Key Laboratory of Tumor Molecular Biology, Jinan University, Guangzhou, China
Correspondence: Ruijun Zhao (ruijunzhao1719@126.com); Wei Xiong (panda_wei_wei@163.com); Hongmei Dong (hmdong0411@126.com)
* Equal contributors to this work.
Received: April 23, 2026
Accepted: July 5, 2026
Published: August 12, 2026
© 2026 The Author(s). Published by GCINC Press, Spokane, Washington, United States. Open Access licensed under a Creative Commons Attribution 4.0 International License (CC BY 4.0), which permits unrestricted use, distribution, and reproduction in any medium, provided the original author(s) and source are credited. To view a copy of this license, visit: Creative Commons Attribution 4.0 International License (CC BY 4.0)
Abstract
Triple-negative breast cancer (TNBC) is characterized by the absence of estrogen receptor (ER), progesterone receptor (PR), and human epidermal growth factor receptor 2 (HER2) expression, limiting the applicability of endocrine and HER2-targeted therapies. Clinically, TNBC exhibits marked molecular heterogeneity, aggressive behavior, early metastatic dissemination, and poor prognosis relative to other breast cancer subtypes. Increasing evidence indicates that the tumor microenvironment (TME) plays a central role in TNBC progression and therapeutic resistance, with exosomes serving as key mediators of intercellular communication. Exosomes, extracellular vesicles measuring 30–150 nm in diameter, are enriched in non-coding RNAs (ncRNAs), including microRNAs (miRNAs), long non-coding RNAs (lncRNAs), and circular RNAs (circRNAs), which regulate interconnected signaling pathways governing proliferation, apoptosis, invasion, epithelial-mesenchymal transition (EMT), angiogenesis, immune evasion, metabolic reprogramming, and therapy resistance. This review synthesizes current evidence on how exosomal ncRNAs orchestrate immune-metabolic networks that shape TNBC evolution and highlights their emerging clinical applications as liquid biopsy biomarkers for diagnosis, prognostic stratification, and therapeutic monitoring, as well as their potential as therapeutic targets via antisense oligonucleotides (ASOs), antagomirs, and engineered exosome-based delivery platforms. Finally, we discuss current translational challenges, including exosome heterogeneity, analytical standardization, and clinical validation, and outline future directions for integrating exosomal ncRNAs into precision management strategies for TNBC.
Keywords
Triple-negative breast cancer; exosomes; non-coding RNAs; tumor microenvironment; immune-metabolic networks; therapeutic resistance; liquid biopsy
1. Introduction
Triple-negative breast cancer (TNBC) is defined by the absence of expression of the estrogen receptor (ER), progesterone receptor (PR), and human epidermal growth factor receptor 2 (HER2), which renders it ineligible for established endocrine and anti-HER2-targeted therapies [1]. This subtype is clinically recognized for its aggressive nature, characterized by a high proliferative index, early metastatic spread, and a generally poor prognosis compared to other breast cancer subtypes [2]. The lack of actionable molecular targets contributes significantly to the therapeutic challenge, leaving systemic chemotherapy as the primary treatment modality with often suboptimal outcomes [3].
The therapeutic landscape has since evolved considerably: immunotherapy (e.g., pembrolizumab), PARP inhibitors (e.g., talazoparib for gBRCA-mutated TNBC), and antibody-drug conjugates (e.g., sacituzumab govitecan) have reshaped selected TNBC treatment settings, including first-line metastatic and high-risk early-stage disease [4-6]. Despite these advances, the heterogeneous and adaptive nature of TNBC continues to underscore the importance of the tumor microenvironment (TME) in tumor evolution and therapeutic resistance [7]. Increasing evidence indicates that the TME actively shapes TNBC evolution; however, the relative contribution of individual stromal, immune, and metabolic components remains highly context-dependent and varies across molecular TNBC subtypes [8, 9]. Among all components of the TME, exosomes represent a critical and indispensable element.
Exosomes are a specific subtype of extracellular vesicles (EVs), typically 30–150 nm in diameter, that originate from the endosomal system and are released into the extracellular space upon fusion of multivesicular bodies (MVBs) with the plasma membrane [10]. Their biogenesis begins with the inward budding of the endosomal membrane to form intraluminal vesicles (ILVs), a process under exquisite control by molecular machinery, including Rab GTPases, SNARE proteins, and ESCRT complexes [11]. The composition of exosomes is a molecular fingerprint of their cell of origin, comprising a lipid bilayer membrane enriched in cholesterol, sphingomyelin, and tetraspanins (e.g., CD9, CD63, CD81), which serve as canonical markers. The lumen encapsulates a diverse cargo of proteins, lipids, and nucleic acids, including DNA, mRNAs, and various classes of non-coding RNAs (ncRNAs) [12]. This selective cargo packaging is not a stochastic process but is governed by specific sorting mechanisms that ensure the stable delivery of functional molecules [13] (Figure 1).
Recent investigations have revealed that exosomes can be secreted by virtually all cell types and are ubiquitously distributed in biological fluids, including blood, urine, saliva, and cerebrospinal fluid, and play pivotal roles under both physiological and pathological conditions [14]. This exosome-mediated communication facilitates the horizontal transfer of oncogenic or tumor-suppressive signals, contributing significantly to TME remodeling and the systemic landscape that favors malignancy [15]. For instance, exosomal circular RNAs (circRNAs) such as circRHCG, derived from TNBC cells, have been shown to reprogram tumor-associated macrophages (TAMs) towards a pro-tumor M2 phenotype via the FUS/BTRC/TFEB axis and exert autocrine pro-proliferative effects [16].
Furthermore, exosomes can deliver ncRNAs that confer therapy resistance, a major clinical hurdle in TNBC management, through mechanisms such as stabilization of HIF-1α, which has been reported to promote glycolysis and chemoresistance [17].
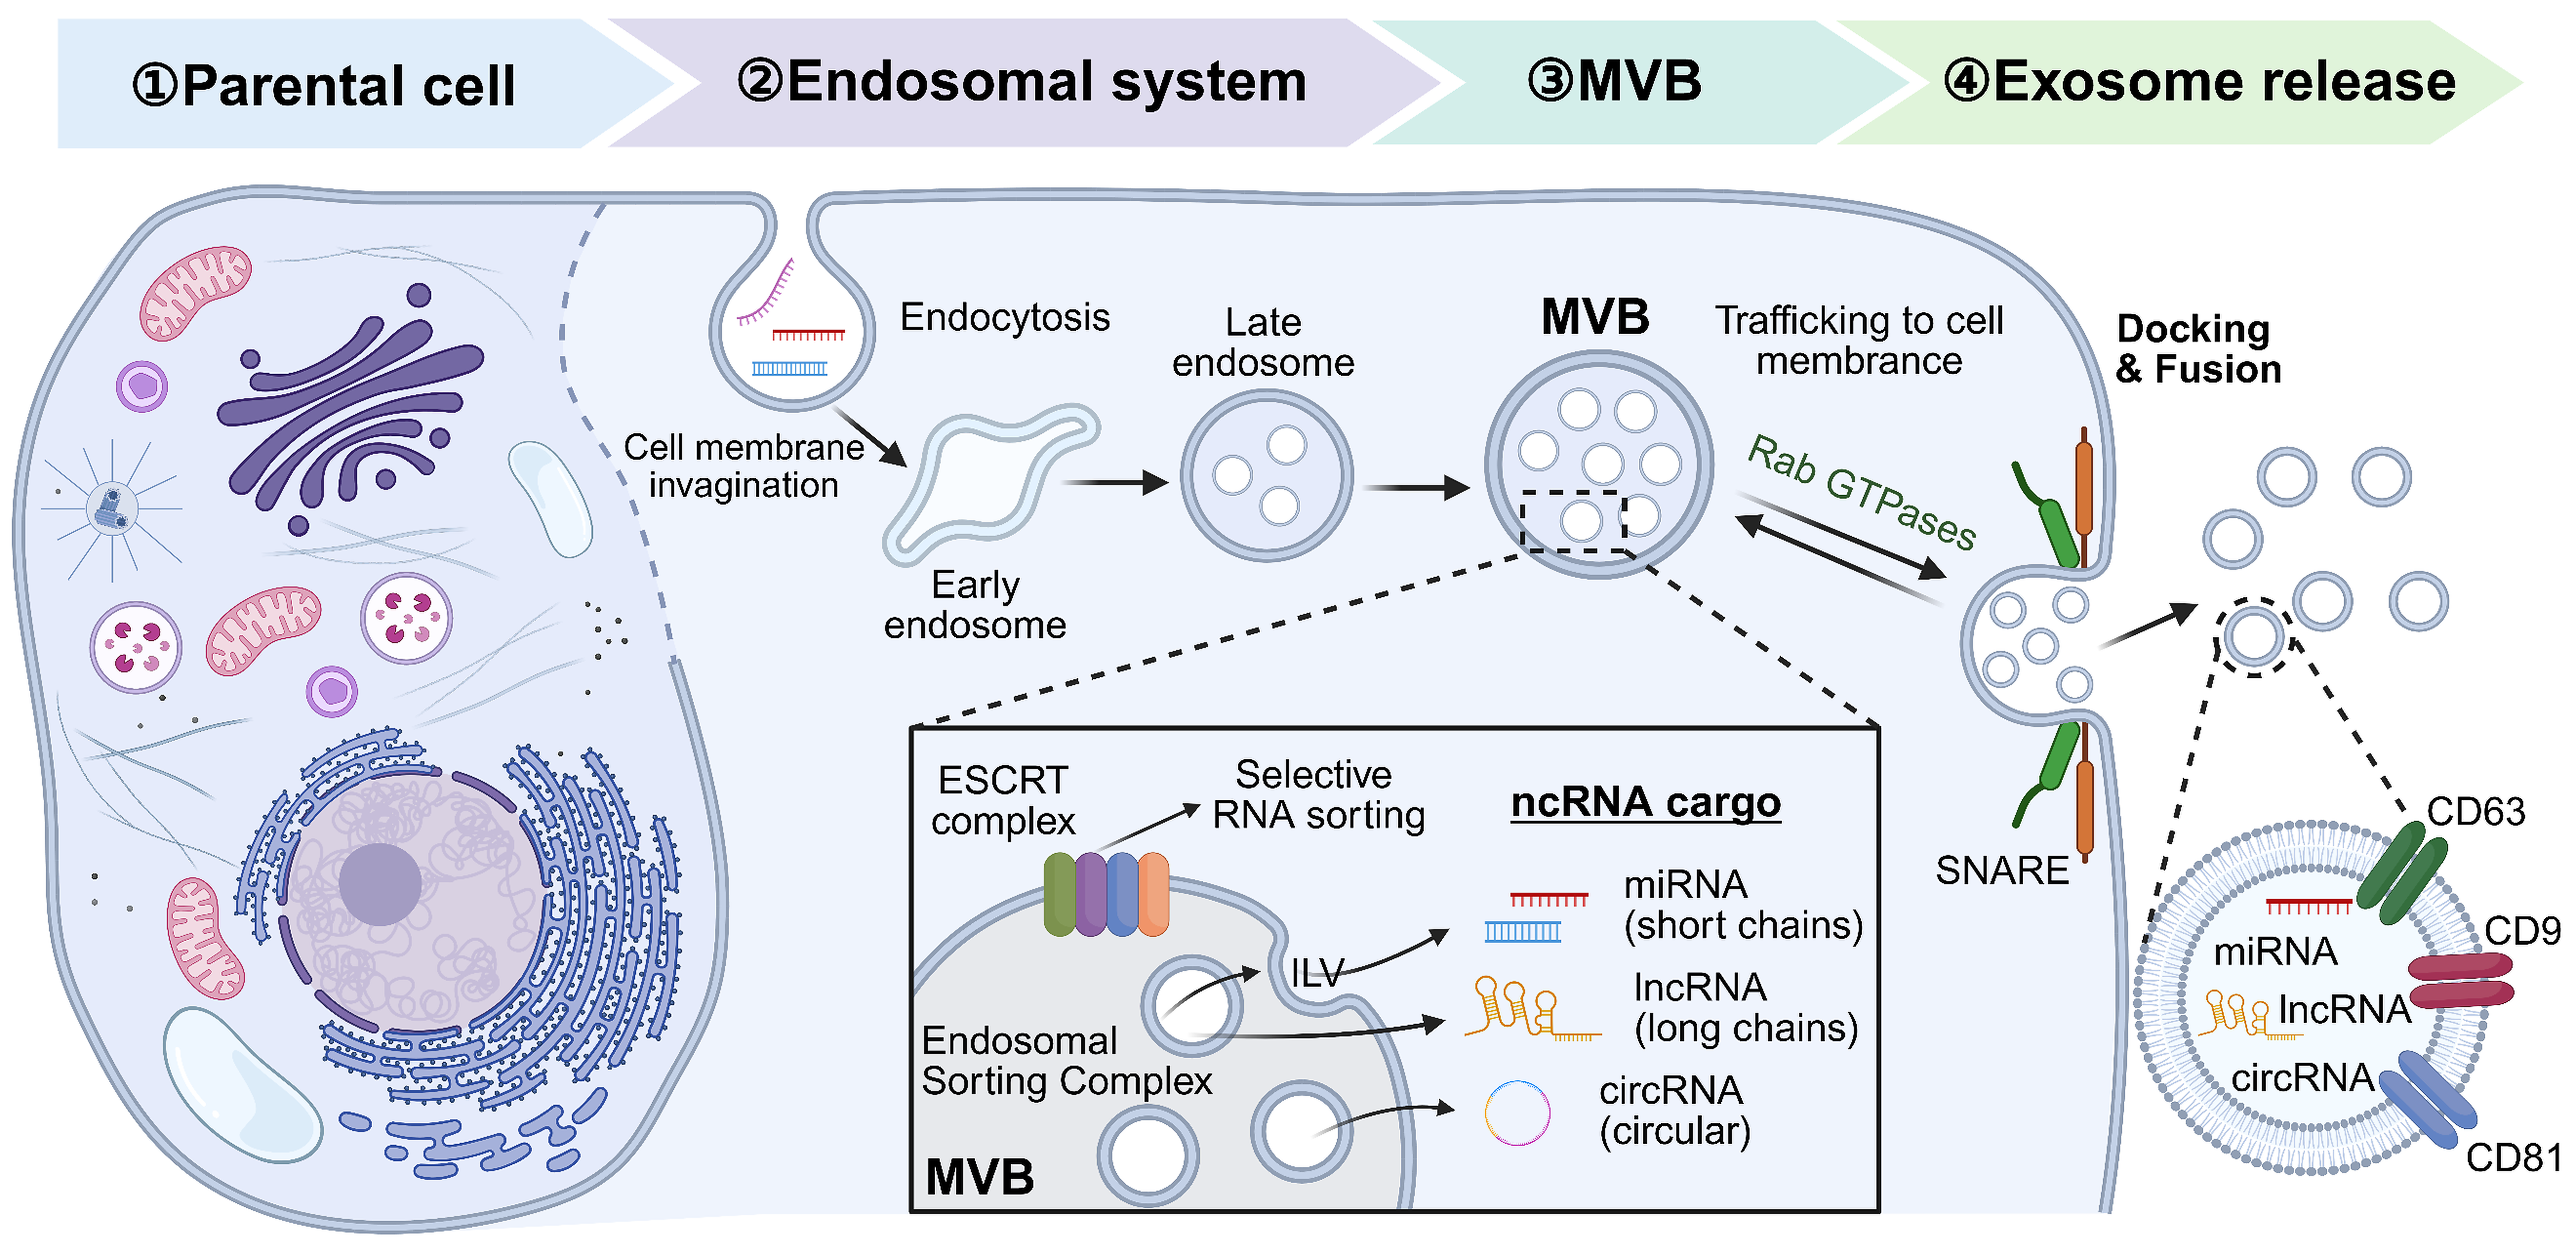
Among the various types of exosomal cargo, ncRNAs are particularly abundant [18]. Dysregulation of ncRNAs has been shown to drive BC progression by promoting proliferation, invasion, metastasis, and tumor cell cachexia [19]. These RNAs are broadly categorized into several major classes based on size, structure, and biogenesis, with microRNAs (miRNAs), long non-coding RNAs (lncRNAs), and circular RNAs being the most extensively studied in cancer biology [20]. miRNAs are small, single-stranded RNAs, typically 20-24 nucleotides in length, that primarily function by binding to complementary sequences in the 3′-untranslated regions (3′-UTRs) of target messenger RNAs (mRNAs), leading to mRNA degradation or translational repression [21].
In contrast, lncRNAs are defined as transcripts longer than 200 nucleotides that lack protein-coding potential and act through diverse mechanisms, including chromatin remodeling, transcriptional regulation, and post-transcriptional modulation [22]. CircRNAs constitute a more recently characterized class of covalently closed, single-stranded RNA loops formed through back-splicing, which confer high stability and allow them to function as microRNA sponges, protein decoys, or templates for translation [23]. The cross-talk and functional interplay between different ncRNA classes, such as lncRNAs sponging miRNAs or circRNAs modulating lncRNA function, create intricate regulatory networks that underpin the aggressive phenotype of TNBC [24]. This functional diversity positions various ncRNAs not only as contributors to malignancy but also as promising candidates for therapeutic intervention. Preclinical studies demonstrate that modulating the expression of specific miRNAs, lncRNAs, or circRNAs using mimics, antagomirs, antisense oligonucleotides (ASOs), or RNA interference (RNAi) strategies can suppress tumor growth, inhibit metastasis, and resensitize TNBC cells to chemotherapy [25].
Collectively, these observations support exosomal ncRNAs as attractive therapeutic candidates; however, whether individual ncRNAs represent true disease drivers or biomarkers of broader tumor evolution remains unresolved. This article elucidates the critical mechanisms by which exosomal ncRNAs regulate the initiation and progression of TNBC, encompassing the promotion of tumor proliferation, invasion, and metastasis, therapeutic resistance, and remodeling of the TME. It further emphasizes the dual clinical utility of exosomal ncRNAs: serving as liquid biopsy biomarkers for early diagnosis and prognostic evaluation and acting as therapeutic targets to enable precise clinical intervention. Overall, this review systematically synthesizes advances in exosomal ncRNAs, from basic research to clinical translation, and identifies novel strategies for the precision diagnosis and treatment of TNBC.
2. Exosomal cargo in TNBC: a focus on ncRNAs
Exosomal miRNAs in TNBC
When packaged into EVs, miRNAs acquire remarkable stability in the extracellular space, functioning as mobile signaling molecules that orchestrate cellular responses across the TME and at distant anatomical sites [13]. In TNBC, accumulating preclinical evidence suggests that exosomal miRNAs not only serve as promising non-invasive liquid biopsy biomarkers but also directly drive malignant processes via intercellular transfer.
At the biomarker level, multiple studies have established exosomal miRNA panels with diagnostic, prognostic, and therapy-predictive value. Comprehensive expression profiling of exosomal miRNAs in TNBC patients revealed that a signature composed of exosomal miR-335, miR-376c, miR-382, and miR-433 was specifically elevated in TNBC subtypes, and that miR-374 levels positively correlated with tumor size. In the same study, a prognostic exosomal miRNA signature consisting of miR-155 and miR-301 effectively predicted pathological complete response to neoadjuvant chemotherapy in TNBC patients [26]. Recent studies have further expanded the repertoire of biomarker signatures and identified a panel of five exosomal miRNAs (hsa-miR-6803, hsa-miR-1180, hsa-miR-4728, hsa-miR-1915, and hsa-miR-940) that exhibited consistently elevated expression across TNBC cell lines, cancer stem cell-like populations, and clinical specimens, demonstrating diagnostic potential [27]. Concurrently, profiling of exosomal miRNAs from TNBC patients undergoing neoadjuvant treatment has revealed dynamic changes associated with therapy [28].
At the functional level, these dysregulated exosomal miRNAs influence key oncogenic processes. The selective enrichment of specific miRNAs within exosomes further amplifies their functional repertoire. Serum exosomal miR-373 levels were significantly elevated in patients with TNBC and hormone receptor-negative breast cancer compared with those with luminal subtypes; this miRNA has been reported to promote an aggressive, therapy-resistant phenotype by downregulating estrogen receptor expression and suppressing drug-induced apoptosis [29]. Functional studies subsequently validated that miR-1180 and miR-4728 from the aforementioned signature markedly enhanced the invasive and migratory capacities of TNBC cells [27], directly corroborating the role of exosomal miRNAs in driving tumor progression.
Beyond tumor-derived miRNAs, exosomal miRNA-mediated stromal-tumor communication is equally critical. For instance, mesenchymal stem cell (MSC)-derived exosomes can transport the oncogenic miRNA miR-106a-5p, thereby promoting TNBC growth [30]. Together, these studies support dual diagnostic and functional roles for exosomal miRNAs, although most evidence derives from relatively small patient cohorts and experimental models requiring independent validation.
Exosomal lncRNAs in TNBC
Exosomal lncRNAs represent an important class of EV-associated ncRNAs involved in TNBC progression. By being enriched in tumor- or stromal cell-derived exosomes, lncRNAs can be transferred between cancer cells and components of the TME, thereby regulating intercellular communication, immune remodeling, metastatic dissemination, and therapy resistance. Their relative stability in circulation also supports their potential application as liquid biopsy biomarkers for disease monitoring and prognostic stratification.
TNBC-associated exosomal lncRNAs contribute to TME remodeling and metastatic progression. For example, tumor-derived exosomal lncRNA MALAT1 stimulates M2 macrophage polarization in the TME by upregulating POSTN and activating the Hippo/YAP signaling axis, thereby fostering an immunosuppressive microenvironment that supports TNBC progression [31]. In addition, tumor-derived exosomal lncRNA SNHG4 is enriched in serum exosomes from TNBC patients and has been reported to promote TNBC cell proliferation and migration by upregulating XPO5 [32]. These findings indicate that exosomal lncRNAs can act as intercellular mediators, reinforcing malignant phenotypes across tumor and stromal compartments, although discerning the specific contribution of exosomal transfer from intracellular lncRNA activity remains a challenge in current experimental systems.
Exosomal lncRNAs also participate in hypoxia-associated immune and metabolic remodeling. Under hypoxic conditions, macrophage-derived exosomal lncRNA MIR210HG upregulates HIF-1α and activates RASSF7 transcription, thereby promoting epithelial-mesenchymal transition (EMT) and metastatic dissemination in TNBC [33]. This macrophage-to-tumor exosomal signaling axis links immune-cell reprogramming with hypoxia-driven tumor adaptation, suggesting that exosomal lncRNAs may participate in immune-metabolic regulatory circuits during TNBC evolution.
In addition to promoting tumor progression, exosomal lncRNAs are involved in the horizontal transmission of therapy-resistant phenotypes. Exosomes derived from docetaxel-resistant TNBC cells are enriched in lncRNA LINC00667. After uptake by sensitive recipient cells, exosomal LINC00667 functions as a competing endogenous RNA by sponging miR-200b-3p, thereby increasing Bcl-2 expression, suppressing apoptosis, and reducing docetaxel sensitivity [34]. This mechanism illustrates how exosomal lncRNAs can disseminate resistance-associated signals between heterogeneous TNBC cell populations.
Therapeutically, lncRNA-centered exosomal strategies may identify actionable vulnerabilities to overcome treatment resistance. Although LINC02544 is better characterized as an immunotherapy-resistance-associated lncRNA than as a naturally transferred exosomal cargo, exosome-based siRNA delivery targeting the LINC02544/miR-497-5p/CAPRIN1 axis has been proposed as a strategy to restore therapeutic responsiveness in TNBC [35]. This example highlights the dual relevance of exosomes in TNBC: they can act as endogenous carriers of pathogenic lncRNAs and can also be engineered as delivery vehicles to silence resistance-associated lncRNA circuits.
The clinical relevance of exosomal lncRNAs is further reflected in their potential as circulating biomarkers. Serum exosomal lncRNA XIST is significantly elevated in patients with recurrent TNBC and has been proposed as a non-invasive biomarker for monitoring recurrence and disease progression [36]. Similarly, serum exosomal lncRNA SUMO1P3 is upregulated in TNBC and is associated with lymphovascular invasion, lymph node metastasis, histological grade, chemotherapy sensitivity, and poor survival, supporting its potential value for prognostic stratification [37]. These circulating exosomal lncRNAs may provide clinically accessible indicators of TNBC aggressiveness, recurrence risk, and therapeutic vulnerability.
Exosomal circRNAs in TNBC
Exosomal circRNAs represent another crucial class of ncRNAs that are emerging as critical regulators in TNBC. Their inherent stability in EVs makes them well-suited to act as ceRNAs, modulating oncogenic pathways via horizontal transfer within the TME [23]. For instance, exosomal circEGFR, an autophagy-responsive circRNA, is significantly upregulated in TNBC cells under nutrient stress and is secreted via exosomes. This exosomal circEGFR can induce autophagy in recipient cells, promoting tumor progression and metastasis, and its levels in plasma-derived exosomes are elevated in breast cancer patients compared with healthy individuals, underscoring its diagnostic potential [38].
The functional repertoire of exosomal circRNAs in TNBC is largely mediated by their ceRNA activity, whereby they sequester specific miRNAs, derepressing target oncogenes [39]. A foundational example is exosomal circPSMA1, which TNBC cells package into exosomes to transfer migratory capabilities to recipient cells and propagate aggressiveness within the TME. Mechanistically, circPSMA1 sponges miR-637 to derepress Akt1 and activate downstream β-catenin/cyclin D1 signaling [40]. Similarly, exosomal circSIPA1L3, whose exosomal packaging is facilitated by EIF4A3, drives TNBC progression by reprogramming glucose metabolism through its ceRNA activity, which stabilizes IGF2BP3 and enhances glycolysis and lactate secretion to fuel tumor growth [41].
Beyond their individual functions, profiling studies highlight the potential of exosomal circRNAs as biomarkers. For instance, circSTIL is highly expressed in TNBC plasma exosomes and correlates with poor prognosis, while its levels decrease upon pirarubicin treatment, indicating its value for diagnostic and therapeutic monitoring [42]. Bioinformatic analysis of these circRNAs suggests they likely function as ceRNAs. Their distinct expression patterns support their investigation as candidate diagnostic biomarkers; however, prospective validation and standardized analytical workflows remain necessary before routine clinical implementation.
tRNA-derived small RNAs in TNBC and their potential exosomal relevance
Beyond the extensively studied miRNAs, lncRNAs, and circRNAs, tRNA-derived small RNAs (tsRNAs), also referred to as tRNA-derived fragments (tRFs), are emerging as a distinct class of small ncRNAs with potential relevance to TNBC biology. tsRNAs are generated through regulated cleavage of mature tRNAs or precursor tRNAs and were previously regarded as random degradation products. Accumulating evidence now indicates that tsRNAs can participate in translational regulation, stress responses, apoptosis, epigenetic modulation, and immune-related processes [43-46]. However, compared with exosomal miRNAs, lncRNAs, and circRNAs, direct evidence for tsRNAs specifically enriched and functionally transferred by TNBC-derived exosomes remains limited.
Current TNBC-related studies mainly support the clinical relevance of tRFs at the tissue or circulating RNA level. Large-scale analyses have shown that tsRNA biogenesis is influenced by the genomic origin of tRNA and that tsRNA-mRNA interactions may exhibit cancer-type specificity. In TNBC, specific tRFs have been reported to be dysregulated in tumor tissues and plasma, with expression profiles associated with recurrence-free survival, suggesting their potential value for recurrence risk stratification [47]. These findings indicate that tRFs may represent an emerging class of TNBC-associated small RNA biomarkers. Nevertheless, tissue- or total plasma-derived tRFs should not be directly equated with exosomal tsRNAs, because their cellular origin, extracellular carrier type, and vesicular localization remain to be experimentally defined.
Evidence from breast cancer EV models suggests that tRNA-derived fragments can be selectively enriched in EV fractions, although these data are not TNBC-specific. For example, 5′-tRNA halves have been reported to accumulate preferentially in breast cancer cell-derived EVs compared with matched intracellular RNA, whereas some other small RNA species are depleted from extracellular fractions [48]. Such observations support the concept that EV-associated small RNA cargo is not merely a passive reflection of intracellular RNA abundance. However, whether analogous selective loading occurs in TNBC-derived exosomes, whether these tsRNAs are protected within the vesicle lumen, and whether they exert functional effects after transfer to recipient tumor, stromal, or immune cells remain unresolved.
Several challenges currently limit the interpretation and clinical translation of tsRNAs in TNBC. First, tsRNA nomenclature and annotation remain inconsistent, and short tRNA-derived reads often map to multiple genomic loci, complicating accurate assignment. Second, extensive tRNA base modifications can introduce reverse transcription and sequencing biases, affecting quantitative reliability. Third, plasma and EV preparations may contain non-vesicular RNA carriers, including ribonucleoprotein complexes, lipoproteins, and platelet-derived contaminants; therefore, candidate tsRNAs should be verified as vesicle-associated and protected within the EV lumen. Finally, functional validation remains insufficient.
Future studies should combine standardized EV isolation, RNase/protease protection assays, EV-subpopulation analysis, and gain- and loss-of-function experiments in recipient TNBC, stromal, and immune cells to resolve the fundamental issue of whether exosomal tsRNAs actively regulate TNBC biology or primarily reflect broader alterations in RNA metabolism. Large prospective TNBC cohorts will also be required to determine whether exosomal tsRNAs can serve as robust biomarkers or therapeutic targets in precision TNBC management [49].
3. Exosomal ncRNAs orchestrate the pathological network of TNBC
TNBC progression appears to arise from coordinated interactions between tumor-intrinsic programs and exosome-mediated communication networks, although the relative importance of individual ncRNA circuits is likely context-dependent. Rather than acting as isolated molecular regulators, exosomal ncRNAs integrate tumor-intrinsic signaling with dynamic remodeling of the TME, thereby reinforcing malignant phenotypes through multi-layered communication circuits. These ncRNAs are selectively packaged into exosomes and transferred between tumor cells and stromal or immune compartments, enabling the propagation of oncogenic signals across heterogeneous cellular populations.
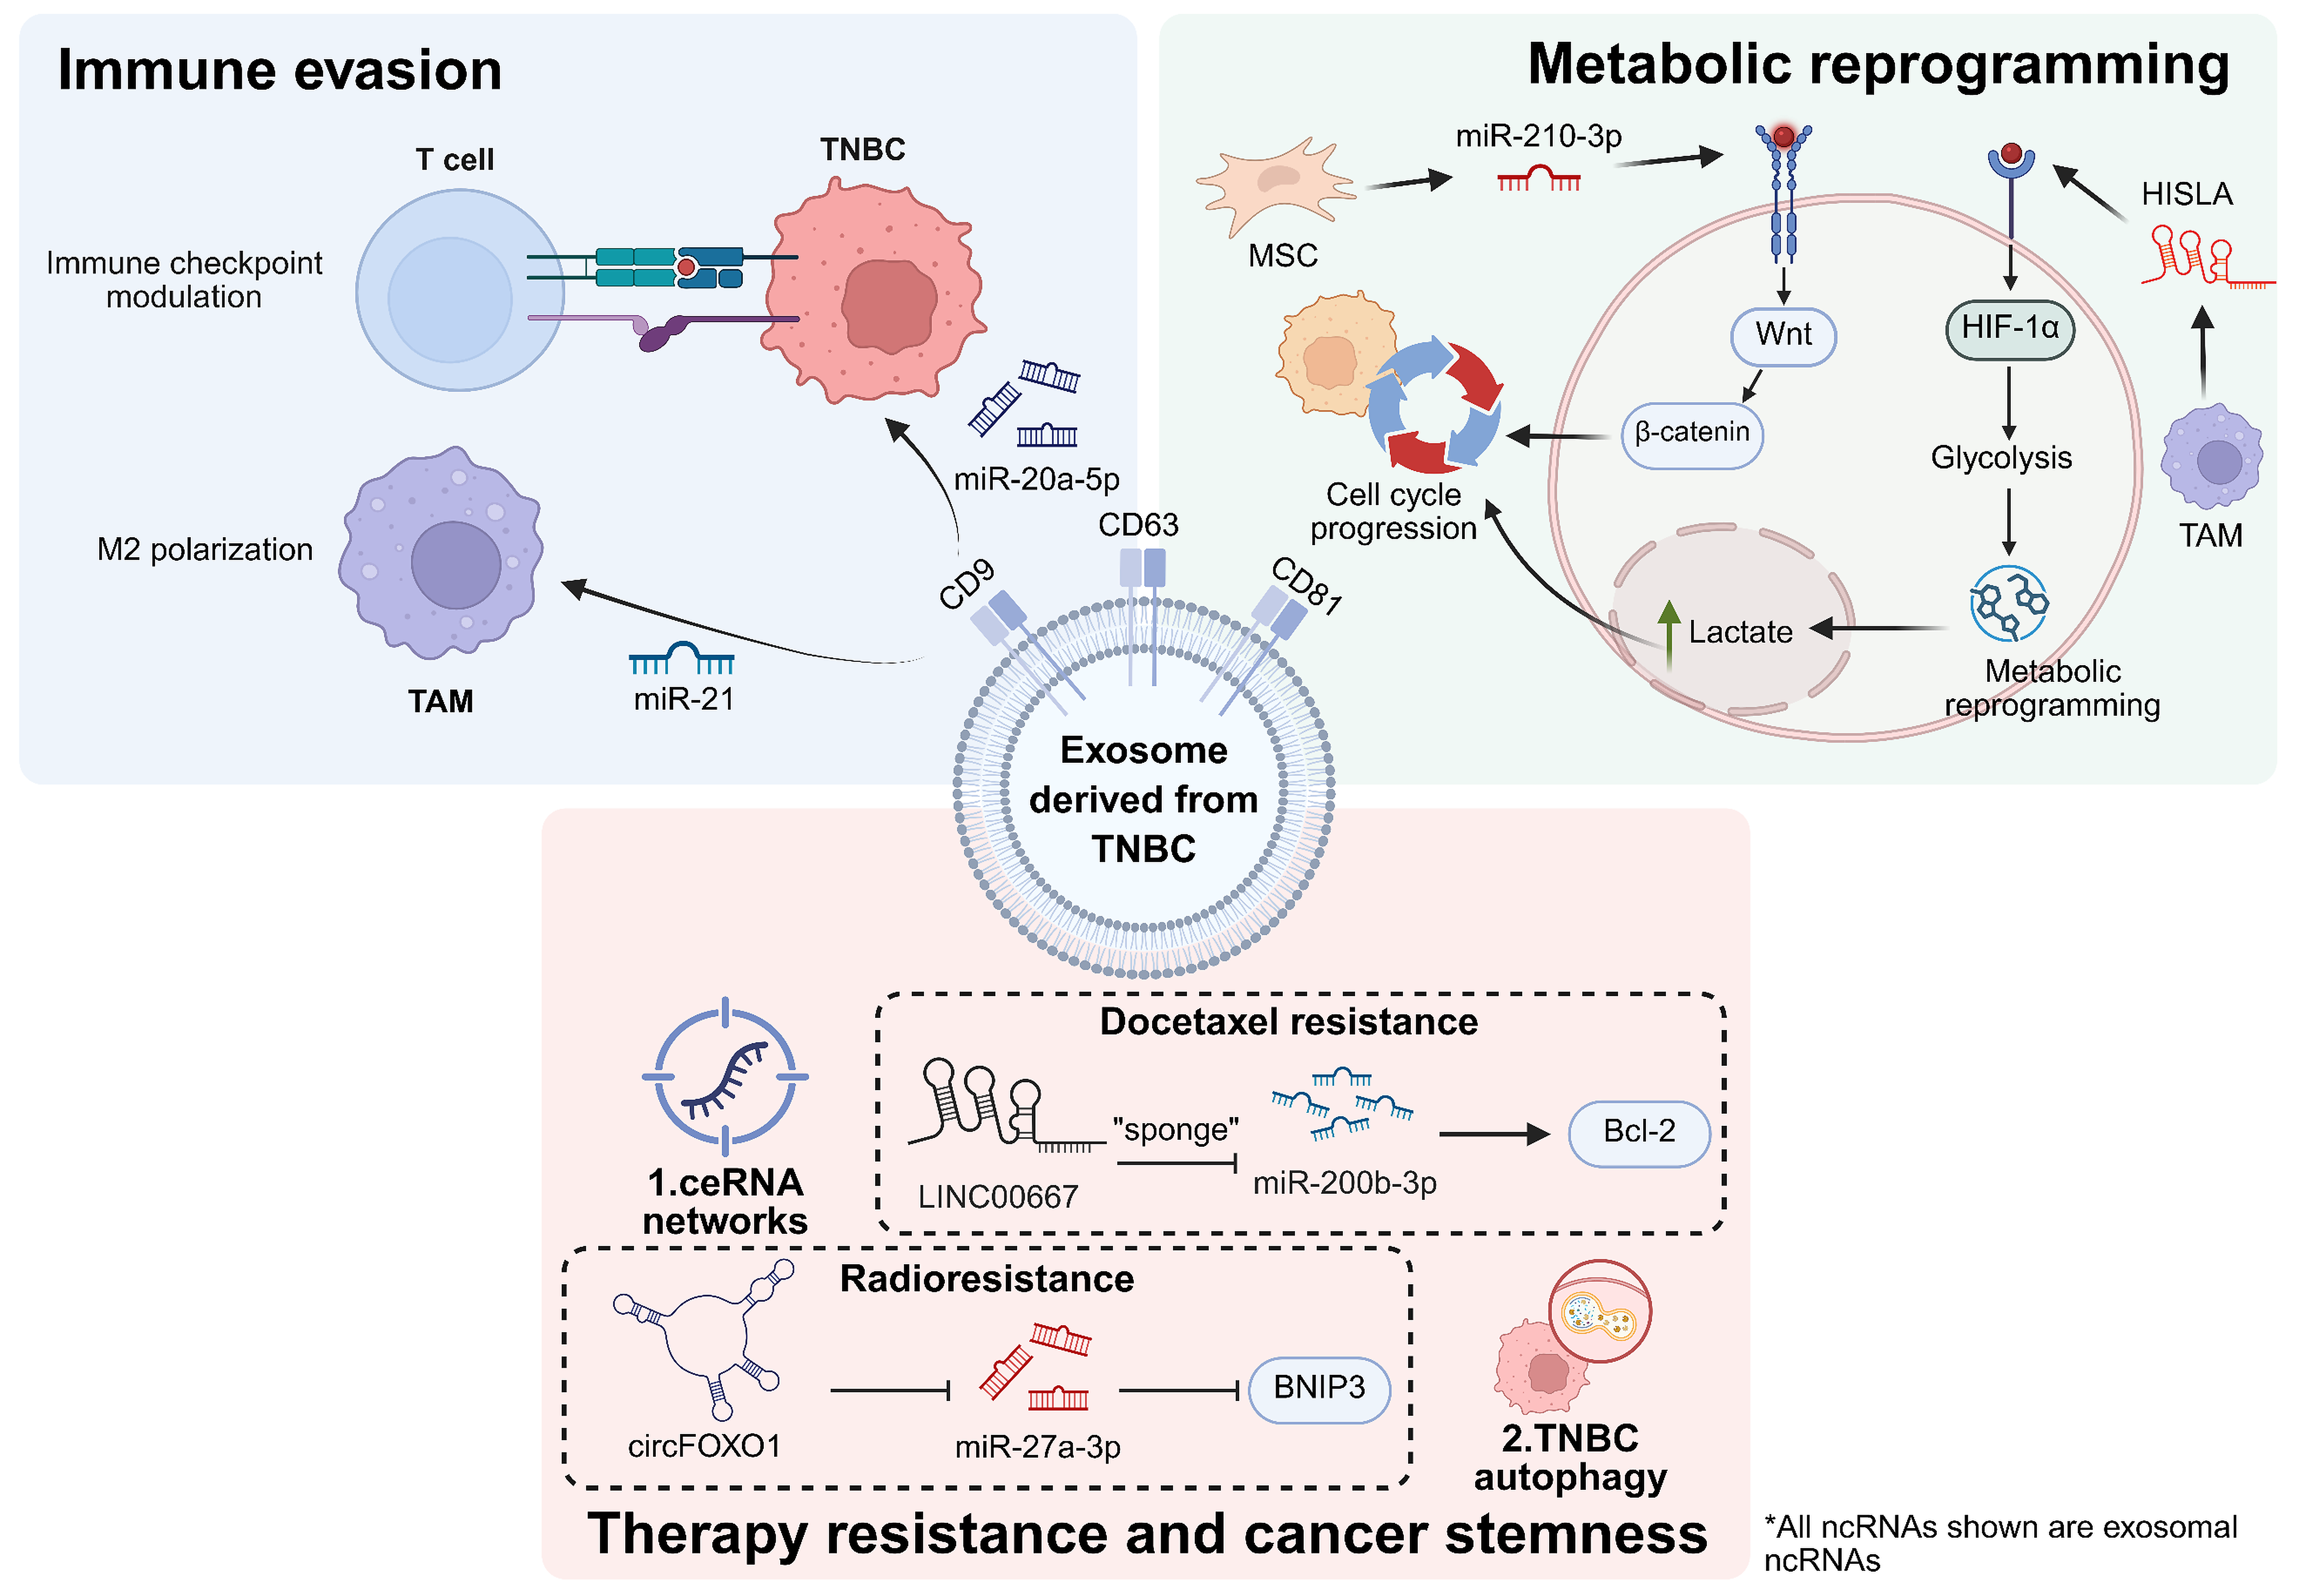
To provide a unifying framework, the functional roles of exosomal ncRNAs in TNBC can be organized into several interconnected biological programs, including oncogenic signaling activation, microenvironmental remodeling, metastatic dissemination, and therapy resistance coupled with cellular plasticity. These programs are not independent; instead, they are linked through continuous feedback interactions that amplify tumor progression and support adaptive evolution under therapeutic pressure. Within this context, individual ncRNAs converge onto a limited number of dominant signaling pathways, including PI3K/AKT, Wnt/β-catenin, HIF-1α-driven metabolic adaptation, and immune regulatory circuits (Figure 2).
Driving oncogenic signaling activation and metabolic reprogramming
Exosomal ncRNAs promote tumor growth and survival primarily by dysregulating central oncogenic signaling pathways and reprogramming metabolism through intercellular transfer. TNBC cell-derived exosomal lncRNA SNHG4 is significantly enriched in serum exosomes from TNBC patients and enhances proliferation and cell cycle progression in recipient cells by upregulating Exportin 5 (XPO5), thereby promoting glycolytic flux and tumor growth [32]. Similarly, exosomal circRNA circRHCG, derived from TNBC cells, not only exerts autocrine pro-proliferative effects on tumor cells but also reprograms TAMs toward a pro-tumor M2 phenotype through the FUS/BTRC/TFEB axis, creating a reciprocal growth-promoting niche [16].
Exosomal ncRNAs critically govern malignant phenotypes through precise regulation of classical signaling cascades. Among these, the PI3K/AKT signaling pathway represents a frequently targeted node by exosomal ncRNAs. For instance, exosomal circPSMA1 released by TNBC cells, upon uptake by recipient cells, can sponge miR-637 to derepress Akt1, subsequently activating downstream β-catenin/cyclin D1 signaling and enhancing proliferative capacity within the TME [40]. In contrast, exosomal miR-145 can suppress angiogenesis in breast cancer MDA-MB-231 cells by targeting IRS1 and inhibiting the IRS1/PI3K/Akt/mTOR axis, highlighting the negative regulatory role of exosomal ncRNAs in modulating this pathway [50]. Furthermore, activation of the Wnt/β-catenin pathway constitutes another critical route through which exosomal ncRNAs enhance proliferation and stem-like characteristics. Under hypoxic conditions, MSC-derived exosomal miR-210-3p activates Wnt/β-catenin signaling via NFIX targeting, thereby inducing EMT and maintaining stemness in recipient TNBC cells [51]. Concurrently, exosomal ncRNAs can also drive the NF-κB pathway, as exemplified by exosomal miR-1910-3p, which may promote proliferation, metastasis, and autophagy of breast cancer cells by targeting MTMR3 and activating NF-κB signaling, revealing another pivotal axis through which exosomal ncRNAs orchestrate classical signaling cascades to drive malignant phenotypes [52].
These signaling perturbations are inextricably linked to metabolic adaptation. TAM-derived exosomal lncRNA HISLA stabilizes HIF-1α in recipient TNBC cells, enhancing glycolysis and anti-apoptotic signaling to promote survival under metabolic stress [17]. Similarly, hypoxic TAM-derived exosomal lncRNA MIR210HG upregulates HIF-1α and activates RASSF7 transcription in recipient tumor cells, driving EMT and metabolic adaptation [33]. Adipocyte-derived exosomal circCRIM1 supports TNBC progression and metastasis by suppressing miR-503-5p to activate OGA, thereby reducing FBP1 stability and functionally linking adipose tissue to tumor metabolic reprogramming [53].
Collectively, these exosome-mediated metabolic programs may contribute to lactate accumulation and immune suppression; however, the magnitude of these effects probably depends on tumor subtype, metabolic state, and stromal composition.
Mediating therapy resistance and cancer stemness
Therapy resistance in TNBC is strongly influenced by exosomal ncRNAs, which facilitate the horizontal transfer of resistance traits and sustain CSC populations. Exosomes derived from resistant cells deliver functional ncRNAs to sensitive cells, reprogramming survival pathways and reducing therapeutic efficacy. For example, exosomal lncRNA LINC00667 increases docetaxel resistance by sponging miR-200b-3p and upregulating Bcl-2, thereby inhibiting apoptosis [34]. The finding illustrates how exosomal lncRNAs can disseminate resistance-associated signals between heterogeneous TNBC cell populations.
Exosomal circRNAs are also critically involved in sustaining CSC populations, which underlie tumor recurrence and resistance. Exosomal circ_0076611 from TNBC cells is transferred to macrophages, where it upregulates TRAF3IP2, promoting M2 polarization and enhancing TNBC invasion and metastasis [54], thereby creating a microenvironment that supports CSC maintenance. Furthermore, exosomal circFOXO1 from CAFs can promote autophagy and radioresistance via the miR-27a-3p/BNIP3 axis [55], indirectly sustaining stemness through enhanced survival signaling. These circRNA‑mediated mechanisms highlight how stromal crosstalk actively preserves CSC reservoirs under therapeutic pressure.
These pathways represent attractive therapeutic targets; however, whether pharmacological modulation can overcome the redundancy of resistance networks in patients remains uncertain. For instance, engineered exosomes loaded with antagomir-155 downregulate oncogenic miR-155 and upregulate its tumor-suppressive target PTEN, thereby suppressing TNBC cell proliferation and restoring chemosensitivity [56].
Therefore, these findings highlight how exosomal ncRNAs integrate survival signaling, metabolic adaptation, and stemness to sustain therapy-resistant phenotypes.
Remodeling the TME and immune evasion
Exosomal ncRNAs are key regulators of tumor-microenvironment interactions, establishing an immunosuppressive and pro-metastatic niche. The TNBC microenvironment comprises diverse stromal and immune cell populations, including cancer-associated fibroblasts (CAFs), TAMs, and MSCs, which are dynamically reprogrammed by exosome-mediated signaling (Figure 3) [57].
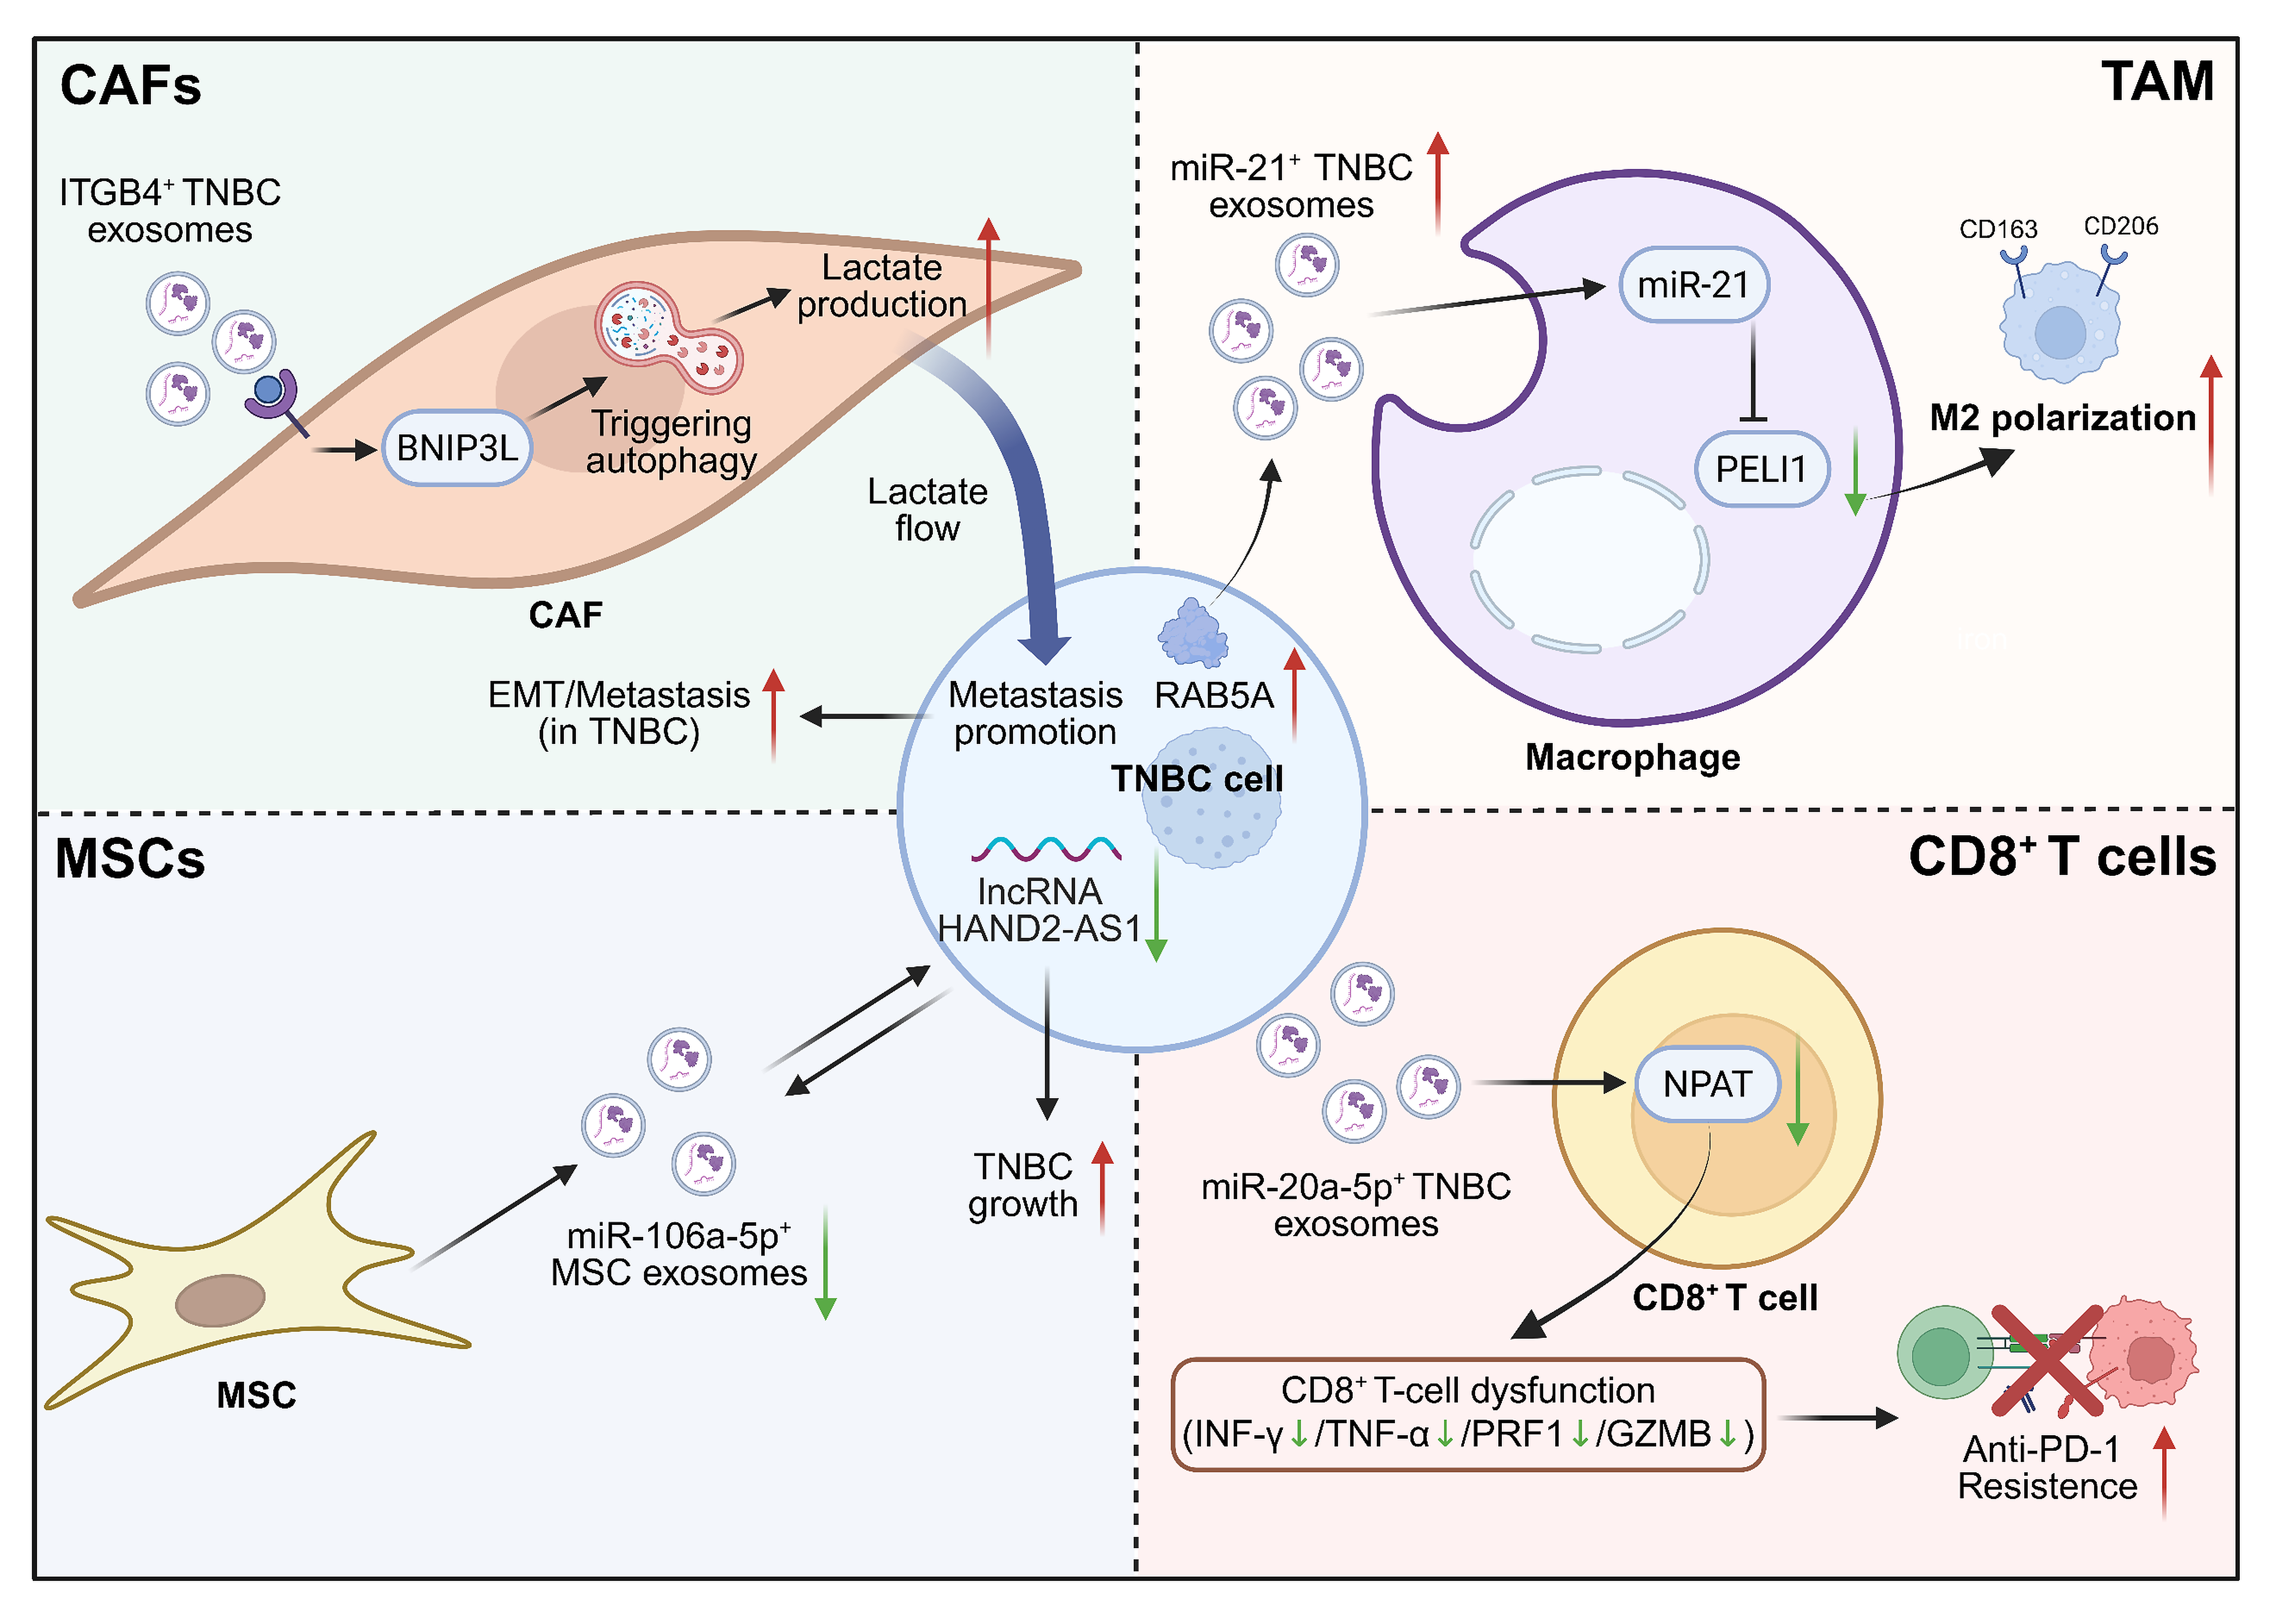
CAFs represent a major stromal component that supports tumor progression [58]. CAF-derived exosomes enriched in miR-500a-5p promote proliferation and metastasis by suppressing USP28 [59]. Meanwhile, CAF exosomal circFOXO1 has been shown to promote TNBC autophagy and radioresistance via the miR-27a-3p/BNIP3 axis, while exosomal circMIB1 encodes MIB1-223aa to stabilize MIB1 and activate DLL4/Notch signaling, collectively driving metastasis and stemness [55, 60]. Conversely, TNBC-derived exosomes transfer ITGB4 to CAFs, thereby inducing BNIP3L-mediated autophagy and lactate production, which support tumor growth and EMT [61]. Additionally, coordinated networks of exosomal miRNAs, including miR-185-5p, miR-652-5p, and miR-1246, regulate fibroblast migration and extracellular matrix remodeling, thereby facilitating metastatic dissemination [62].
Macrophages constitute another critical component of the TME. Exosomal ncRNAs promote M2 polarization, thereby supporting tumor growth and suppressing immune responses. For example, TNBC cell-derived exosomal miR-21, whose secretion is regulated by RAB5A, suppresses PELI1 expression in macrophages and potentiates M2 polarization, thereby reshaping the tumor immune microenvironment [63]. Similarly, exosomal circRNA circRHCG induces M2 polarization and correlates with poor prognosis [16], while TAM-derived exosomal lncRNA HISLA stabilizes HIF-1α and enhances glycolysis and anti-apoptotic signaling in tumor cells [17]. Moreover, hypoxic TAM-derived exosomal lncRNA MIR210HG upregulates HIF-1α to initiate RASSF7 transcription, thereby promoting EMT and TNBC metastasis [33].
In contrast to the tumor‑promoting functions of CAF‑ and TAM‑derived exosomes, MSC‑derived exosomal ncRNAs can directly suppress malignant phenotypes in recipient TNBC cells, highlighting the therapeutic potential of engineered exosomes. For example, MSC‑derived exosomal miR‑381‑3p inhibits EMT, migration, and invasion in TNBC cells [64]. Human umbilical cord mesenchymal stem cell (HUCMSC)-derived exosomal miR‑3182 induces apoptosis and suppresses proliferation and migration by targeting the mTOR/S6KB1 pathway [65], whereas MSC‑derived exosomal 7SK impairs viability, proliferation, and tumorigenicity [66]. These findings underscore the dual role of exosomal ncRNAs in TNBC. Endogenous tumor-derived exosomes predominantly propagate oncogenic signaling and metabolic reprogramming, whereas engineered MSC-derived exosomes loaded with tumor‑suppressive ncRNAs offer a promising strategy for precision intervention. Importantly, engineered exosomes currently remain substantially more advanced than endogenous exosome-targeting strategies, highlighting an important translational imbalance within the field.
Exosomal ncRNAs also directly modulate immune checkpoint pathways and immunotherapy response. TNBC cell-derived exosomal miR-20a-5p increases immunotherapy resistance by targeting NPAT to induce CD8+ T cell dysfunction, reducing IFN-γ, TNF-α, perforin, and granzyme B production [67], while tumor-suppressive lncRNAs such as HAND2-AS1 regulate bidirectional communication between stromal and tumor cells by reducing MSC-derived exosomal miR-106a-5p secretion [30]. Other regulatory pathways, including the lncRNA LINC02544, which increases immunotherapy resistance through the miR-497-5p/CAPRIN1 axis [35], further illustrate the complexity of immune modulation in TNBC.
Immune-metabolic coupling
The preceding sections have cataloged exosomal ncRNAs according to their discrete oncogenic outputs: metabolic reprogramming, therapy resistance, cancer stemness, and immune evasion. Yet these processes are not modular; they converge upon a central biological nexus that we term immune-metabolic coupling. In TNBC, metabolic reprogramming and immune modulation are two sides of the same coin, and exosomal ncRNAs function as the molecular currency circulating between these domains, establishing a self-reinforcing ecosystem [68, 69].
Exosomal ncRNAs transmit metabolic programs that sculpt immune functionality in TNBC. Tumor-derived exosomal circPSMA1 facilitates tumorigenesis, metastasis, and migration in TNBC through the miR-637/Akt1/β-catenin (cyclin D1) axis, implicating exosomal circRNAs in metabolic reprogramming and proliferative signaling [40]. Concurrently, exosomal circSIPA1L3-mediated intercellular communication contributes to glucose metabolic reprogramming and TNBC progression by enhancing glycolytic flux and lactate efflux, acidifying the microenvironment, and fostering immunosuppressive conditioning [41]. The resulting lactate-rich niche not only fuels tumor progression but also erects a potent immunosuppressive barrier, linking metabolic flux directly to immune evasion.
Beyond metabolic reprogramming of the tumor cell itself, exosomal ncRNAs actively recruit stromal and immune cells into the immune-metabolic ecosystem. Hypoxic CAFs release exosomal circSTAT3 that propagates hypoxic metabolic signatures to TNBC cells, driving cancer stemness via the miR-671-5p/NOTCH1 axis [70]. Conversely, tumor cells dispatch exosomal ncRNAs to subvert immune surveillance: exosomal miR-182-5p directly targets Notch1 in TAMs, reprogramming them into pro-tumorigenic phenotypes [71], while exosomal miR-20a-5p incapacitates CD8+ T-cell cytotoxicity and precipitates resistance to anti-PD-1 therapy [67]. These findings illustrate that exosomal ncRNAs do not merely transmit metabolic programs; they forge a bidirectional communication network in which metabolic stress and immune evasion are reciprocally reinforced.
Recognizing immune-metabolic coupling as an integrated regulatory framework may provide a useful conceptual model; however, direct experimental evidence establishing causal exosomal ncRNA circuits remains limited. Future strategies should aim to disrupt the exosomal circuits that weld these programs together.
Notably, these immune-metabolic coupling nodes, orchestrated by exosomal ncRNAs, represent previously unrecognized clinical vulnerabilities in TNBC, as they are both functionally critical and therapeutically accessible. Engineered exosomes loaded with dual-function ncRNA modulators that simultaneously inhibit glycolytic enzymes and restore T cell metabolism represent a next-generation precision approach. Moreover, liquid biopsy profiling of circulating exosomal ncRNAs that reflect both metabolic activity and immune status may enable dynamic monitoring of the immune metabolic state in real time, guiding the rational design of combinatorial metabolic-immunotherapy trials in TNBC.
4. Clinical significance of exosomal ncRNAs in TNBC
Due to their ability to carry tumor-specific molecules and their stability in body fluids, exosomes have emerged as promising candidates for clinical translation, although analytical standardization and regulatory qualification remain major barriers [72]. Furthermore, their advantages, including low immunogenicity, low toxicity, a prolonged circulation half-life, and the ability to cross biological barriers (such as the blood-brain barrier), along with their capacity to be efficiently loaded with effector molecules, demonstrate their therapeutic potential as novel delivery vehicles [73, 74].
Consequently, translational research on exosomes has accelerated progress in the diagnosis and treatment of TNBC, offering new avenues for biomarker development and the optimization of therapeutic strategies [75]. Based on current research, exosomal ncRNAs in TNBC hold clinical promise across three primary avenues: biomarker development, precision therapeutic intervention, and modulation of therapeutic resistance (Table 1).
Table 1. Exosomal ncRNA-associated biomarkers and therapeutic strategies with potential clinical relevance in TNBC
| Clinical Application | ncRNA | ncRNA type | Source | Clinical significance | Refs |
|---|---|---|---|---|---|
| Biomarker | miR-155, miR-301 | miRNA | Serum | Predicts pCR | (26) |
| Biomarker | miR-373 | miRNA | Serum | Elevated in ER-/PR- tumors; outperforms circulating miR-373 | (29) |
| Biomarker | XIST | lncRNA | Serum | Reduced after surgery; elevated at recurrence; associated with poor OS | (36) |
| Biomarker | SUMO1P3 | lncRNA | Serum | Correlates with LVI, LN metastasis, grade, chemosensitivity; independent prognostic marker | (37) |
| Biomarker | circSTIL | circRNA | Plasma | Distinguishes TNBC from non-TNBC | (42) |
| Biomarker | miR-1910-3p | miRNA | Serum | Superior diagnostic performance to CA15-3 | (52) |
| Biomarker | miR-150-5p, miR-576-3p, miR-4665-5p | miRNA | Plasma | Associated with breast cancer recurrence | (76) |
| Biomarker | miR-939 | miRNA | Serum | Elevated in basal-like TNBC; associated with poor prognosis | (77) |
| Biomarker | miR-221-3p, miR-196a-5p, miR-17-5p, miR-126-3p | miRNA | Cisplatin-treated TNBC cells | Predictive biomarkers of CSC-like cisplatin-resistant TNBC | (78) |
| Therapeutic intervention | miR-155 | miRNA | Engineered exosomes | Suppresses tumor growth | (56) |
| Therapeutic intervention | miR-381-3p | miRNA | HMSCs | Suppresses TNBC aggressiveness | (64) |
| Therapeutic intervention | miR-3182 | miRNA | HUCMSCs | Induces apoptosis; inhibits proliferation and migration | (65) |
| Therapeutic intervention | 7SK | lncRNA | HMSCs | Inhibits viability, proliferation, and tumorigenicity | (66) |
| Therapeutic intervention | miR-424-5p | miRNA | AT-MSCs | Downregulates PD-L1; increases apoptosis and antitumor immunity | (79) |
| Therapeutic intervention | miR-159 | miRNA | Engineered exosomes with doxorubicin | Suppresses tumor proliferation | (80) |
| Reverse therapeutic resistance | LINC00667 | lncRNA | TNBC cell culture supernatant | Targeting LINC00667 reverses docetaxel resistance | (34) |
| Reverse therapeutic resistance | circFOXO1 | circRNA | CAFs | Targeting circFOXO1 enhances radiosensitivity | (55) |
| Reverse therapeutic resistance | miR-342-3p | miRNA | HMSCs | Suppresses metastasis and chemoresistance | (81) |
| Reverse therapeutic resistance | DARS-AS1 | lncRNA | HEK293T cell supernatant | Inhibits autophagy; reverses doxorubicin resistance | (82) |
Abbreviations: AT-MSCs, adipose tissue-derived mesenchymal stromal cells; CAFs, cancer-associated fibroblasts; CA15-3, carbohydrate antigen 15-3; CSC, cancer stem cell; ER, estrogen receptor; HMSCs, human mesenchymal stem cells; HUCMSCs, human umbilical cord mesenchymal stem cells; LN, lymph node; lncRNA, long non-coding RNA; LVI, lymphovascular invasion; miRNA, microRNA; ncRNA, non-coding RNA; OS, overall survival; pCR, pathological complete response; PD-L1, programmed death-ligand 1; PR, progesterone receptor; TNBC, triple-negative breast cancer.
Figure 4 summarizes the multifaceted roles of exosomal ncRNAs in TNBC, illustrating their contributions to tumor initiation and progression, metastatic dissemination, therapeutic resistance, and modulation of the tumor microenvironment.
The figure also highlights the emerging clinical applications of exosomal ncRNAs as minimally invasive biomarkers for diagnosis, prognosis, and treatment monitoring, as well as their potential as therapeutic targets and delivery vehicles in the development of ncRNA-based precision medicine strategies for TNBC.
Exosomal ncRNAs as biomarkers for TNBC
Conventional diagnostic modalities, including mammography, ultrasonography, and localized biopsy, are often associated with radiation exposure or invasive procedures and have limited diagnostic accuracy. Liquid biopsy, as a non-invasive approach, facilitates serial sampling and offers significant advantages in clinical cancer prognosis, metastasis assessment, and recurrence monitoring [13]. Exosomal ncRNAs hold substantial potential for non-invasive diagnosis and early detection of recurrence in TNBC, with compositional and expression alterations that reflect tumor status in real time, thereby enabling dynamic disease surveillance [83].
Exosomal miRNA expression profiles are intimately associated with TNBC clinicopathological characteristics and risk factors, providing a foundation for disease diagnosis. A study analyzed 45 miRNAs in exosomes from 435 breast cancer patients and identified 17 aberrantly expressed miRNAs in the TNBC subgroup (n = 224) compared with healthy women, with 18 exosomal miRNAs differentially expressed between HER2-positive breast cancer and TNBC. Univariate and multivariate models demonstrated that exosomal miR-155 and miR-301 were the most predictive of pathological complete response [26]. In addition, 20 upregulated and 34 downregulated exosomal miRNAs were identified in TNBC patients, among which elevated miR-150-5p, miR-576-3p, and miR-4665-5p were associated with breast cancer recurrence [76]. Exosomal miR-939 is highly expressed in basal-like tumor subtypes and correlates with an unfavorable prognosis in TNBC [77]. Serum exosomal miR-1910-3p serves as an effective diagnostic biomarker, with significantly superior diagnostic performance compared with the conventional tumor marker CA15-3; the combined application of these markers substantially improves TNBC diagnostic sensitivity [52]. Furthermore, investigation of cisplatin-treated TNBC cells revealed that an exosomal miRNA cluster (miR-221-3p, miR-196a-5p, miR-17-5p, and miR-126-3p), together with downstream markers, may serve as prognostic/predictive biomarkers associated with CSC-like subpopulations [78].
Notably, exosome-carried lncRNAs exhibit substantial prognostic potential by enabling dynamic disease monitoring and recurrence prediction. Serum exosomal lncRNA SUMO1P3 is significantly upregulated in TNBC patients and closely associated with lymphovascular invasion, lymph node metastasis, and chemotherapy sensitivity, serving as an independent prognostic factor for unfavorable survival [37]. Serum exosomal XIST levels decline following primary tumor resection but rise upon recurrence, with elevated levels significantly associated with inferior overall survival, highlighting its utility for post-treatment surveillance [36]. Serum exosomal lncRNA DANCR is strongly correlated with advanced TNM stage and distant metastasis, serving as an independent adverse prognostic indicator [84]. Comprehensive exosome-related lncRNA profiling studies have identified robust prognostic signatures. A 15-exosome-related lncRNA risk signature was identified through TCGA analysis and demonstrated good performance in predicting overall survival and immunotherapy responsiveness, with AUC values exceeding 0.7 [85]. Furthermore, an exosome-based gene signature (ALCAM, FAM129B, GNB2, KRT6A, PGK1, SERPINE1, THY1) constructed for TNBC achieved one-, three-, and five-year OS AUC values all exceeding 0.85, accurately estimating clinical outcomes and predicting response to docetaxel and immune checkpoint blockade [86]. Thus far, the vast majority of published biomarker studies remain retrospective in design and are constrained by limited cohort sizes, emphasizing the need for large-scale prospective multicenter validation before clinical adoption.
Therapeutic strategies targeting exosomal ncRNAs in TNBC
One direct strategy against exosome-mediated pathogenic signaling is to neutralize oncogenic ncRNAs with ASOs and antagomirs, thereby restoring the normal regulatory network of recipient cells [25]. ASOs are typically used to target lncRNAs and mRNAs, while antagomirs are chemically modified antagonists specifically designed to silence miRNAs [87]. A key challenge for ASOs and antagomirs is achieving efficient and specific delivery to tumor cells while minimizing systemic toxicity and degradation. Interestingly, exosomes, which are often the source of the pathogenic signal, also provide a solution to this delivery hurdle as natural, biocompatible nanocarriers. For instance, a study demonstrated the feasibility of loading an antagomir against oncogenic miR-155 into exosomes via electroporation. Treatment of TNBC cells (MDA-MB-231) with these engineered exosomes resulted in significant downregulation of miR-155 and a consequent upregulation of its tumor-suppressive target PTEN [56]. This proof-of-concept highlights a dual role for exosomes: as a pathogenic entity to target and as a therapeutic vehicle to deliver silencing agents.
Another strategy involves harnessing exosomes as endogenous nanoscale vesicles, which possess inherent advantages that make them highly attractive as natural delivery vehicles for therapeutic ncRNAs in TNBC. Although exosomes offer low immunogenicity, high biocompatibility, and biological barrier penetration that enhance delivery and reduce the off-target effects of therapeutic nucleic acids compared with synthetic vectors, their manufacturing reproducibility, loading efficiency, and biodistribution remain incompletely optimized. [88]. The engineering of exosomes involves loading them with tumor-suppressive ncRNAs, such as miRNAs or small interfering RNAs (siRNAs), targeting oncogenes, and often modifying their surface to achieve targeted delivery to TNBC cells [13].
Native exosomes loaded with therapeutic ncRNAs can directly suppress tumor progression. For instance, MSC-derived exosomes that deliver miR-342-3p inhibit TNBC metastasis and chemoresistance by modulating ID4 [81]. To further enhance targeting precision, surface modification strategies have been widely adopted; EGFR-targeting aptamer CL4-modified exosomes efficiently deliver siRNA-DARS-AS1, resensitizing cells to doxorubicin via inhibition of autophagy [82], and folate-modified exosomes loaded with the ferroptosis inducer erastin demonstrate superior antiproliferative and antimigratory effects against MDA-MB-231 cells [89]. Building upon these approaches, co-delivery systems augment therapeutic efficacy through synergistic action; exosomes co-loaded with cholesterol-modified miR-159 and doxorubicin hydrochloride cooperatively suppress tumor proliferation by silencing TCF-7 [80], whereas exosome-mediated delivery of miR-424-5p suppresses PD-L1 signaling, induces an inflammatory microenvironment, and enhances tumor cell apoptosis, offering a novel strategy for immunotherapy [79]. Additionally, CAR-T cell-derived exosomes retain surface CAR and CD3 complexes, specifically targeting MSLN-positive TNBC cells to inhibit tumor growth in vivo with high efficacy and without systemic toxicity [90], highlighting the unique advantages of genetically engineered cell-derived exosomes.
Overcoming therapeutic resistance via exosomal ncRNA modulation
While engineered exosomes offer a promising platform for delivering therapeutic ncRNAs to TNBC cells, a significant clinical challenge lies in the inherent and acquired resistance to conventional chemotherapies. Exosomal ncRNAs are pivotal mediators of the development and propagation of this chemoresistance, and their targeted modulation offers a viable strategy to resensitize tumors to conventional therapies. A key mechanism involves the horizontal transfer of resistance-conferring lncRNAs via exosomes from drug-resistant to drug-sensitive cells. For instance, exosomes derived from docetaxel-resistant TNBC cells are enriched in lncRNA LINC00667. Upon uptake by sensitive cells, this exosomal LINC00667 acts as a ceRNA to sponge miR-200b-3p, leading to the upregulation of the anti-apoptotic protein Bcl-2 and, consequently, reducing the chemosensitivity of recipient cells to docetaxel [34]. In addition, SOD1-high CAFs secrete exosomal miR-3960, which targets BRSK2 in TNBC cells to suppress PIMREG phosphorylation at S16, thereby activating NF-κB signaling and promoting cisplatin resistance [91]. Therapeutic intervention aimed at silencing such oncogenic exosomal lncRNAs can therefore reverse drug resistance. This is exemplified by epidermal growth factor receptor (EGFR)-targeted aptamer CL4-modified exosomes (EXOs-CL4) that deliver siRNA targeting the lncRNA DARS-AS1. Silencing DARS-AS1 suppressed autophagy, thereby attenuating doxorubicin resistance and enhancing antitumor efficacy in TNBC models [82].
Beyond targeting resistance pathways within cancer cells, modulating exosomal ncRNA signaling can rewire the TME from a pro- to an anti-tumor state, indirectly overcoming therapeutic barriers. TNBC cell-derived exosomes can drive this polarization; for example, exosomal circ_0076611 from TNBC cells is transferred to macrophages, where it upregulates TRAF3IP2, promoting M2 polarization and enhancing TNBC invasion and metastasis [54]. Disrupting this exosomal communication, perhaps by inhibiting exosomal packaging or release of circ_0076611, represents a strategy to prevent M2 polarization, restore immune surveillance, and potentially sensitize tumors to therapy. However, given that multiple resistance mechanisms frequently coexist within individual tumors, modulation of a single exosomal ncRNA alone is unlikely to achieve durable therapeutic benefit.
Clinical translation barriers and single-vesicle technological innovations
Despite promising preclinical efficacy, the clinical translation of exosomal ncRNA therapeutics for TNBC faces formidable manufacturing and technical hurdles. Large-scale purification of clinical-grade exosomes remains inefficient; current gold-standard methods, including ultracentrifugation [92], size-exclusion chromatography [93], and tangential flow filtration [94], suffer from low throughput, co-isolation of protein aggregates and lipoproteins, and progressive loss of vesicle integrity during concentration [95]. Batch-to-batch consistency is further undermined by source-cell heterogeneity, as donor age, passage number, and culture oxygen tension substantially alter exosomal RNA cargo profiles [96]. Drug loading efficiency presents another critical obstacle: passive incubation of hydrophilic nucleic acids such as antagomirs or siRNAs yields poor encapsulation rates, whereas active loading via electroporation, while superior for cargo incorporation [97], risks ncRNA aggregate formation, membrane disruption, and non-specific cargo contamination [98], ultimately compromising vesicle stability and in vivo biodistribution. Consequently, rigorous quality control metrics are indispensable, encompassing transmission electron microscopy for morphological verification, nanoparticle tracking analysis for size distribution, and functional knockdown validation in reporter cells, to ensure that therapeutic potency and membrane integrity are preserved from production to administration [99].
Emerging high-resolution technologies offer a path toward resolving these bottlenecks by shifting exosomal ncRNA analysis from bulk populations to the single-vesicle level. Nano-flow cytometry now enables multiparametric profiling of individual EVs down to approximately 40 nm in diameter, directly correlating surface markers with the abundance of internal cargo [100]. Single-vesicle imaging modalities, such as super-resolution microscopy and interferometric scattering, enable visualization of the spatial distribution of ncRNAs without ensemble averaging [101]. Complementarily, droplet digital PCR (ddPCR) achieves absolute quantification of low-abundance ncRNA copies per vesicle, exceeding the sensitivity limits of conventional qPCR [102]. Integration of these platforms with microfluidic isolation chips will enable single-vesicle liquid biopsies that distinguish tumor-derived from benign exosomes in real time [103], thereby ensuring both diagnostic precision and manufacturing fidelity for therapeutic exosome batches. These advances will be critical for determining whether resistance-associated ncRNAs are selectively enriched in tumor-secreted exosomes and for establishing the standardized good manufacturing practice (GMP) frameworks required for routine clinical application. Future regulatory approval will likely require harmonized manufacturing standards, potency assays, and reproducible release criteria across production platforms.
5. Discussion
Functionally, exosomes secreted by parental cells serve as critical mediators of intercellular communication within the TME and systemic circulation. By selectively packaging and delivering diverse ncRNAs to recipient cells, exosomes orchestrate dynamic reprogramming of the TME. Collectively, current evidence supports a central role for exosomal ncRNAs in TNBC biology; however, the field remains dominated by mechanistic preclinical studies rather than prospective clinical validation (Table 2). Furthermore, aberrant alterations in exosomal ncRNA expression profiles provide highly promising liquid biopsy biomarkers for early screening, precise prognostic assessment, and real-time monitoring of treatment responses in TNBC.
Table 2. Expression patterns and mechanistic roles of ncRNAs in TNBC
| ncRNA type | ncRNA | Expression | Target(s) | Biological function | Refs |
|---|---|---|---|---|---|
| miRNA | miR-1180, miR-4728 | Upregulation | n.d. | Promotes migration and invasion | (27) |
| miR-373 | Upregulation | ER | Promotes invasion and therapy resistance | (29) | |
| miR-185-5p, miR-652-5p, miR-1246 | Upregulation | n.d. | Fibroblast migration and ECM remodeling | (62) | |
| miR-21 | Upregulation | PELI1 | Promotes TAM polarization | (63) | |
| miR-381-3p | Deregulation | n.d. | Inhibits EMT, migration, and invasion | (64) | |
| miR-3182 | Deregulation | mTOR, S6KB1 | Inhibits proliferation and migration and promotes apoptosis | (65) | |
| miR-424-5p | Deregulation | PD-L1 | Promotes apoptosis | (79) | |
| miR-342-3p | Deregulation | ID4 | Inhibits metastasis and chemoresistance | (81) | |
| miR-3960 | Deregulation | BRSK2 | Promotes cisplatin resistance | (91) | |
| lncRNA | HISLA | Upregulation | HIF-1α | Promotes glycolysis and inhibits apoptosis | (17) |
| HAND2-AS1 | Deregulation | RUNX2 | Inhibitsproliferation | (30) | |
| MALAT1 | Upregulation | POSTN | Promotes TAM polarization | (31) | |
| SNHG4 | Upregulation | XPO5 | Promotes proliferation and migration | (32) | |
| MIR210HG | Upregulation | HIF-1α | Promotes EMT and metastasis | (33) | |
| LINC00667 | Upregulation | miR-200b-3p, Bcl-2 | Promotes docetaxel resistance | (34) | |
| LINC02544 | Upregulation | miR-497-5p, CAPRIN1 | Promotes immunotherapy resistance | (35) | |
| 7SK | Deregulation | HMGA1 | Inhibits proliferation, migration and invasion | (66) | |
| circRNA | circRHCG | Upregulation | FUS, BTRC, TFEB axis | Promotes TAM polarization | (16) |
| circEGFR | Upregulation | miR-224-5p, ATG13, ULK1 | Promotes autophagy | (38) | |
| circSTIL | Upregulation | n.d. | Promotes proliferation, migration and invasion | (42) | |
| circ_0076611 | Upregulation | TRAF3IP2 | Promotes TAM polarization | (54) | |
| circFOXO1 | Upregulation | miR-27a-3p, BNIP3 axis | Promotes autophagy and radioresistance | (55) | |
| circMIB1 | Upregulation | MIB1-223aa | Promotes metastasis and stemness | (60) |
Abbreviations: Bcl-2, B-cell lymphoma 2; BRSK2, BR serine/threonine kinase 2; CAF, cancer-associated fibroblast; CAPRIN1, cell cycle-associated protein 1; ECM, extracellular matrix; EMT, epithelial-mesenchymal transition; ER, estrogen receptor; FUS, fused in sarcoma; HIF-1α, hypoxia-inducible factor-1α; HMGA1, high mobility group AT-hook 1; ID4, inhibitor of DNA binding 4; lncRNA, long non-coding RNA; mTOR, mechanistic target of rapamycin; ncRNA, non-coding RNA; PD-L1, programmed death-ligand 1; PELI1, pellino E3 ubiquitin protein ligase 1; POSTN, periostin; RUNX2, runt-related transcription factor 2; S6KB1, ribosomal protein S6 kinase B1; TAM, tumor-associated macrophage; TFEB, transcription factor EB; TRAF3IP2, TRAF3 interacting protein 2; XPO5, exportin 5; n.d., not determined.
Despite extensive characterization of exosomal ncRNAs, a central unresolved issue is whether these molecules act as dominant drivers of TNBC progression or merely reflect tumor state. This ambiguity is compounded by the remarkable heterogeneity of EV subpopulations, which differ in biogenesis, size, and cellular origin, making it difficult to attribute specific functional outcomes to particular ncRNA species [104]. Moreover, the extent to which ncRNA loading into exosomes occurs through active sorting versus passive stochastic incorporation remains poorly defined [105], further blurring the line between causal agency and correlative bystander effects. Current bulk analytical approaches also lack the temporal resolution needed to establish whether changes in exosomal ncRNA profiles precede or follow shifts in tumor behavior, while conventional in vivo models often fail to preserve the full complexity of the TME, leaving the directionality of intercellular communication unresolved. Clarifying this fundamental question will ultimately depend on integrating single-vesicle-resolution omics, standardized isolation workflows, and patient-derived lineage-tracing systems that can dissect driver functions from passenger phenomena in a spatiotemporally faithful manner [106]. Whether observed exosomal ncRNA signatures reflect tumor evolution, treatment selection, or adaptive host responses is likely to differ among clinical contexts.
However, current research is methodologically far from achieving this integration; the resulting divergence has hindered mechanistic consensus across studies, thereby directly constraining the prioritization of translational efforts. Divergent isolation protocols, inconsistent quantification metrics, and variable reporting standards have collectively produced a fragmented literature in which comparable findings remain elusive, thereby eroding confidence in the reproducibility of exosomal ncRNA signatures [107]. The absence of consensus on whether observed ncRNA alterations represent cause or consequence further complicates the rational design of therapeutic interventions, as candidate targets selected under the driver hypothesis may in fact be epiphenomenal byproducts of tumor evolution [108]. Additionally, the field continues to grapple with the technical challenge of distinguishing vesicle-specific ncRNA signals from background contamination, a limitation that undermines the specificity required for robust biomarker validation [109]. Overcoming these barriers will require adopting standardized frameworks such as the MISEV2023 guidelines, implementing orthogonal analytical strategies, and conducting large-scale, multicenter prospective cohorts to establish definitive causal links between exosomal ncRNA dynamics and TNBC progression [110-112].
In clinical translation, the specific targeting of exosomal ncRNAs for therapeutic purposes remains a major hurdle. While silencing oncogenic ncRNAs like LINC00667 can sensitize TNBC cells to chemotherapy, delivering inhibitors such as ASOs or siRNAs specifically to tumor cells and their exosomal communication pathways in vivo remains inefficient [113]. Similarly, although exosomes are promising natural delivery vehicles, controlling their biodistribution, minimizing clearance, and ensuring targeted release of therapeutic cargo to TNBC cells are significant engineering challenges. This is compounded by the need to overcome multiple, often overlapping, resistance mechanisms mediated by exosomal ncRNAs, which contribute not only to chemoresistance but also to radioresistance, a critical issue in TNBC management [109, 114]. Importantly, improvements in mechanistic understanding should not automatically be interpreted as immediate therapeutic opportunities, as biological feasibility and clinical tractability frequently diverge.
At the same time, clinically driven solutions arising from unmet medical needs should be emphasized. TNBC patients currently face a critical gap in real-time treatment monitoring tools, as conventional imaging and tissue biopsy cannot capture the dynamic evolution of therapeutic resistance or minimal residual disease in a non-invasive manner [115]. The heterogeneity in assay platforms and the absence of standardized protocols further complicate the reproducibility of exosomal ncRNA signatures across laboratories, eroding confidence in their clinical utility [107]. Additionally, the unresolved question of whether exosomal ncRNAs actively drive resistance or merely report on tumor adaptation has profound implications for therapeutic decision-making: if they are passive reporters, liquid biopsy strategies can be optimized for monitoring; if they are active drivers, they become targets for intervention. Bridging this gap will require prospective longitudinal cohorts that integrate multi-parametric liquid biopsy approaches with robust clinical endpoints, ultimately translating basic mechanistic insights into actionable clinical tools for personalized TNBC management.
Furthermore, current TNBC molecular classification systems largely operate in parallel rather than converging, leaving clinicians without an integrated algorithm to navigate the interplay among genomic subtype, immune contexture, and dynamic disease evolution [116, 117]. The static nature of conventional tissue-based profiling further amplifies this disconnect, as it fails to capture the temporal heterogeneity of tumors under therapeutic pressure, limiting real-time treatment adaptation. Moreover, the absence of validated composite scoring systems that weight molecular subtype, immune biomarkers, and homologous recombination status precludes the rational prioritization of available therapeutic modalities, leaving patient selection reliant on a trial-and-error approach. Future efforts must move beyond cataloging individual biomarkers toward establishing multidimensional stratification frameworks that integrate transcriptomic subtype, genomic scar signatures, immune microenvironment indices, and liquid biopsy-derived dynamic markers into a unified decision-support algorithm, validated through prospective umbrella trials [118].
In summary, although exosomal ncRNAs demonstrate substantial potential in TNBC research, the intricate molecular mechanisms underlying their roles, technical bottlenecks in isolation and characterization, and heterogeneity across studies remain critical challenges to be addressed. Future progress will likely depend on integrating standardized exosome isolation, single-vesicle technologies, spatial multi-omics, longitudinal liquid biopsy cohorts, and mechanistic validation in clinically relevant models. Such studies will be essential to distinguish causal exosomal ncRNA networks from surrogate biomarkers and to define where therapeutic intervention is most likely to benefit patients.
References
1. Unuofin JO, Adefisan-Adeoye AO, Paimo OK, Maphetu N, Lebelo SL. Breast cancer: epidemiology, molecular classification, diagnostics and evolving treatment paradigms. Molecules. 2026;31(14):2551. https://doi.org/10.3390/molecules31142551
2. Mei J, Hao L, Wang H, Xu R, Liu Y, Zhu Y, et al. Systematic characterization of non-coding RNAs in triple-negative breast cancer. Cell Prolif. 2020;53(5):e12801. https://doi.org/10.1111/cpr.12801
3. Bianchini G, Balko JM, Mayer IA, Sanders ME, Gianni L. Triple-negative breast cancer: challenges and opportunities of a heterogeneous disease. Nat Rev Clin Oncol. 2016;13(11):674–690. https://doi.org/10.1038/nrclinonc.2016.66
4. Shah M, Osgood CL, Amatya AK, Fiero MH, Pierce WF, Nair A, et al. FDA approval summary: pembrolizumab for neoadjuvant and adjuvant treatment of patients with high-risk early-stage triple-negative breast cancer. Clin Cancer Res. 2022;28(24):5249–5253. https://doi.org/10.1158/1078-0432.Ccr-22-1110
5. Rugo HS, Ettl J, Hurvitz SA, Gonçalves A, Lee KH, Fehrenbacher L, et al. Outcomes in clinically relevant patient subgroups from the EMBRACA study: talazoparib vs physician's choice standard-of-care chemotherapy. JNCI Cancer Spectr. 2020;4(1):pkz085. https://doi.org/10.1093/jncics/pkz085
6. Tolaney SM, de Azambuja E, Kalinsky K, Loi S, Kim SB, Yam C, et al. Sacituzumab govitecan plus pembrolizumab for advanced triple-negative breast cancer. N Engl J Med. 2026;394(4):354–366. https://doi.org/10.1056/NEJMoa2508959
7. Kudelova E, Smolar M, Holubekova V, Hornakova A, Dvorska D, Lucansky V, et al. Genetic heterogeneity, tumor microenvironment and immunotherapy in triple-negative breast cancer. Int J Mol Sci. 2022;23(23):14937. https://doi.org/10.3390/ijms232314937
8. Panada E, Kuznetsova T, Hamilton S. Unlocking the tumor microenvironment: innovative strategies for cancer therapy and translational insights. Cell Rep Med. 2025;6(11):102468. https://doi.org/10.1016/j.xcrm.2025.102468
9. Peng X, Zheng J, Liu T, Zhou Z, Song C, Geng Y, et al. Tumor microenvironment heterogeneity, potential therapeutic avenues, and emerging therapies. Curr Cancer Drug Targets. 2024;24(3):288–307. https://doi.org/10.2174/1568009623666230712095021
10. Goh CY, Wyse C, Ho M, O'Beirne E, Howard J, Lindsay S, et al. Exosomes in triple-negative breast cancer: garbage disposals or Trojan horses? Cancer Lett. 2020;473:90–97. https://doi.org/10.1016/j.canlet.2019.12.046
11. Tomasetti M, Lee W, Santarelli L, Neuzil J. Exosome-derived microRNAs in cancer metabolism: possible implications in cancer diagnostics and therapy. Exp Mol Med. 2017;49(1):e285. https://doi.org/10.1038/emm.2016.153
12. Lakshmi S, Hughes TA, Priya S. Exosomes and exosomal RNAs in breast cancer: a status update. Eur J Cancer. 2021;144:252–268. https://doi.org/10.1016/j.ejca.2020.11.033
13. Fan Q, Yang L, Zhang X, Peng X, Wei S, Su D, et al. The emerging role of exosome-derived non-coding RNAs in cancer biology. Cancer Lett. 2018;414:107–115. https://doi.org/10.1016/j.canlet.2017.10.040
14. Zhou R, Chen KK, Zhang J, Xiao B, Huang Z, Ju C, et al. The decade of exosomal long RNA species: an emerging cancer antagonist. Mol Cancer. 2018;17(1):75. https://doi.org/10.1186/s12943-018-0823-z
15. Di Agostino S, Vahabi M, Turco C, Fontemaggi G. Secreted non-coding RNAs: functional impact on the tumor microenvironment and clinical relevance in triple-negative breast cancer. Noncoding RNA. 2022;8(1):5. https://doi.org/10.3390/ncrna8010005
16. Shen HY, Xu JL, Zhang W, Chen QN, Zhu Z, Mao Y. Exosomal circRHCG promotes breast cancer metastasis via facilitating M2 polarization through TFEB ubiquitination and degradation. NPJ Precis Oncol. 2024;8(1):22. https://doi.org/10.1038/s41698-024-00507-y
17. Chen F, Chen J, Yang L, Liu J, Zhang X, Zhang Y, et al. Extracellular vesicle-packaged HIF-1α-stabilizing lncRNA from tumour-associated macrophages regulates aerobic glycolysis of breast cancer cells. Nat Cell Biol. 2019;21(4):498–510. https://doi.org/10.1038/s41556-019-0299-0
18. Tosar JP, Buck AH. mGem: guides or triggers? Extracellular RNAs beyond vesicular miRNAs. mBio. 2025;16(10):e0312924. https://doi.org/10.1128/mbio.03129-24
19. Peng J, Liu W, Tian J, Shu Y, Zhao R, Wang Y. Non-coding RNAs as key regulators of epithelial-mesenchymal transition in breast cancer. Front Cell Dev Biol. 2025;13:1544310. https://doi.org/10.3389/fcell.2025.1544310
20. Márton É, Varga A, Domoszlai D, Buglyó G, Balázs A, Penyige A, et al. Non-coding RNAs in cancer: structure, function, and clinical application. Cancers (Basel). 2025;17(4):579. https://doi.org/10.3390/cancers17040579
21. Bartel DP. MicroRNAs: target recognition and regulatory functions. Cell. 2009;136(2):215–233. https://doi.org/10.1016/j.cell.2009.01.002
22. Yousefi H, Maheronnaghsh M, Molaei F, Mashouri L, Aref AR, Momeny M, et al. Long noncoding RNAs and exosomal lncRNAs: classification and mechanisms in breast cancer metastasis and drug resistance. Oncogene. 2020;39(5):953–974. https://doi.org/10.1038/s41388-019-1040-y
23. Xu A, Zhu L, Yao C, Zhou W, Guan Z. The therapeutic potential of circular RNA in triple-negative breast cancer. Cancer Drug Resist. 2024;7:13. https://doi.org/10.20517/cdr.2023.141
24. Paul U, Banerjee S. The functional significance and cross-talk of non-coding RNAs in triple-negative and quadruple-negative breast cancer. Mol Biol Rep. 2022;49(7):6899–6918. https://doi.org/10.1007/s11033-022-07288-2
25. Scaratti GP, Miranda IMA, Nunes-Souza E, Ruthes MO, Rosolen D, Fonseca AS, et al. Non-coding RNA-based therapeutic strategies in triple-negative breast cancer: a systematic review. Int J Mol Sci. 2026;27(4):1882. https://doi.org/10.3390/ijms27041882
26. Stevic I, Müller V, Weber K, Fasching PA, Karn T, Marmé F, et al. Specific microRNA signatures in exosomes of triple-negative and HER2-positive breast cancer patients undergoing neoadjuvant therapy within the GeparSixto trial. BMC Med. 2018;16(1):179. https://doi.org/10.1186/s12916-018-1163-y
27. Choudhary A, Poojary SS, Jain P, Chaturvedi H, Das BC. Identification of novel exosomal miRNAs and their role in diagnosis and prognosis of triple-negative breast cancer. BMC Cancer. 2026;26(1):210. https://doi.org/10.1186/s12885-025-15499-6
28. Sueta A, Fujiki Y, Goto-Yamaguchi L, Tomiguchi M, Yamamoto-Ibusuki M, Iwase H, et al. Exosomal miRNA profiles of triple-negative breast cancer in neoadjuvant treatment. Oncol Lett. 2021;22(6):819. https://doi.org/10.3892/ol.2021.13080
29. Eichelser C, Stückrath I, Müller V, Milde-Langosch K, Wikman H, Pantel K, et al. Increased serum levels of circulating exosomal microRNA-373 in receptor-negative breast cancer patients. Oncotarget. 2014;5(20):9650–9663. https://doi.org/10.18632/oncotarget.2520
30. Xing L, Tang X, Wu K, Huang X, Yi Y, Huan J. LncRNA HAND2-AS1 suppressed the growth of triple-negative breast cancer via reducing secretion of MSC-derived exosomal miR-106a-5p. Aging (Albany NY). 2021;13(1):424–436. https://doi.org/10.18632/aging.202148
31. Wang X, Jian Q, Zhang Z, Gu J, Wang X, Wang Y. Effect of tumor-derived extracellular vesicle-shuttled lncRNA MALAT1 on proliferation, invasion and metastasis of triple-negative breast cancer by regulating macrophage M2 polarization via the POSTN/Hippo/YAP axis. Transl Oncol. 2024;49:102076. https://doi.org/10.1016/j.tranon.2024.102076
32. Wang ZW, Yang HS, Guo HS, Li YY, Zhong JY, Jiang S, et al. Tumor-derived exosomal lncRNA SNHG4 promotes triple-negative breast cancer progression by targeting XPO5. Front Oncol. 2025;15:1593827. https://doi.org/10.3389/fonc.2025.1593827
33. Feng L, Wang Y, Wang X, Li B, Liu Y, Zhang W, et al. Exosomal lncRNA MIR210HG derived from hypoxic TAMs promotes the metastasis of triple-negative breast cancer. Int Immunopharmacol. 2025;165:115416. https://doi.org/10.1016/j.intimp.2025.115416
34. Li J, Kang J, Liu W, Liu J, Pan G, Mao A, et al. Docetaxel-resistant triple-negative breast cancer cell-derived exosomal lncRNA LINC00667 reduces the chemosensitivity of breast cancer cells to docetaxel via targeting miR-200b-3p/Bcl-2 axis. Eur J Histochem. 2022;66(4):3529. https://doi.org/10.4081/ejh.2022.3529
35. Lian B, Li J, Tang S, Li T, Li J. Targeting LINC02544/miR-497-5p/CAPRIN1 axis via exosome-based siRNA to overcome immunotherapy resistance in triple-negative breast cancer. Mol Med. 2025;31(1):278. https://doi.org/10.1186/s10020-025-01336-w
36. Lan F, Zhang X, Li H, Yue X, Sun Q. Serum exosomal lncRNA XIST is a potential non-invasive biomarker to diagnose recurrence of triple-negative breast cancer. J Cell Mol Med. 2021;25(16):7602–7607. https://doi.org/10.1111/jcmm.16009
37. Na-Er A, Xu YY, Liu YH, Gan YJ. Upregulation of serum exosomal SUMO1P3 predicts unfavorable prognosis in triple-negative breast cancer. Eur Rev Med Pharmacol Sci. 2021;25(1):154–160. https://doi.org/10.26355/eurrev_202101_24379
38. Song H, Zhao Z, Ma L, Zhao W, Hu Y, Song Y. Novel exosomal circEGFR facilitates triple-negative breast cancer autophagy via promoting TFEB nuclear trafficking and modulating miR-224-5p/ATG13/ULK1 feedback loop. Oncogene. 2024;43(11):821–836. https://doi.org/10.1038/s41388-024-02950-4
39. Lyu L, Zhang S, Deng Y, Wang M, Deng X, Yang S, et al. Regulatory mechanisms, functions, and clinical significance of CircRNAs in triple-negative breast cancer. J Hematol Oncol. 2021;14(1):41. https://doi.org/10.1186/s13045-021-01052-y
40. Yang SJ, Wang DD, Zhong SL, Chen WQ, Wang FL, Zhang J, et al. Tumor-derived exosomal circPSMA1 facilitates the tumorigenesis, metastasis, and migration in triple-negative breast cancer (TNBC) through miR-637/Akt1/β-catenin (cyclin D1) axis. Cell Death Dis. 2021;12(5):420. https://doi.org/10.1038/s41419-021-03680-1
41. Liang Y, Ye F, Luo D, Long L, Wang Y, Jin Y, et al. Exosomal circSIPA1L3-mediated intercellular communication contributes to glucose metabolic reprogramming and progression of triple-negative breast cancer. Mol Cancer. 2024;23(1):125. https://doi.org/10.1186/s12943-024-02037-4
42. Ji J, Li M, Yan K, Ma J, Wei D, Zhang F, et al. circSTIL mediates pirarubicin inhibiting the malignant phenotype of triple-negative breast cancer and acts as a biomarker in plasma exosomes. Mol Immunol. 2025;180:86–95. https://doi.org/10.1016/j.molimm.2025.02.014
43. Cole C, Sobala A, Lu C, Thatcher SR, Bowman A, Brown JWS, et al. Filtering of deep sequencing data reveals the existence of abundant Dicer-dependent small RNAs derived from tRNAs. RNA. 2009;15(12):2147–2160. https://doi.org/10.1261/rna.1738409
44. Yamasaki S, Ivanov P, Hu GF, Anderson P. Angiogenin cleaves tRNA and promotes stress-induced translational repression. J Cell Biol. 2009;185(1):35–42. https://doi.org/10.1083/jcb.200811106
45. Thompson DM, Lu C, Green PJ, Parker R. tRNA cleavage is a conserved response to oxidative stress in eukaryotes. RNA. 2008;14(10):2095–2103. https://doi.org/10.1261/rna.1232808
46. Anderson P, Ivanov P. tRNA fragments in human health and disease. FEBS Lett. 2014;588(23):4297–4304. https://doi.org/10.1016/j.febslet.2014.09.001
47. Feng W, Li Y, Chu J, Li J, Zhang Y, Ding X, et al. Identification of tRNA-derived small noncoding RNAs as potential biomarkers for prediction of recurrence in triple-negative breast cancer. Cancer Med. 2018;7(10):5130–5144. https://doi.org/10.1002/cam4.1761
48. Tosar JP, Gámbaro F, Sanguinetti J, Bonilla B, Witwer KW, Cayota A. Assessment of small RNA sorting into different extracellular fractions revealed by high-throughput sequencing of breast cell lines. Nucleic Acids Res. 2015;43(11):5601–5616. https://doi.org/10.1093/nar/gkv432
49. Hussain MS, Zhang L, Ashique S. Extracellular vesicles-associated tRFs as emerging biomarkers in breast cancer. Curr Cancer Drug Targets. 2025;25(10):1200–1209. https://doi.org/10.2174/0115680096388071250527074008
50. Pan S, Zhao X, Shao C, Fu B, Huang Y, Zhang N, et al. STIM1 promotes angiogenesis by reducing exosomal miR-145 in breast cancer MDA-MB-231 cells. Cell Death Dis. 2021;12(1):38. https://doi.org/10.1038/s41419-020-03304-0
51. Wang M, Zheng Y, Hao Q, Mao G, Dai Z, Zhai Z, et al. Hypoxic BMSC-derived exosomal miR-210-3p promotes progression of triple-negative breast cancer cells via NFIX-Wnt/β-catenin signaling axis. J Transl Med. 2025;23(1):39. https://doi.org/10.1186/s12967-024-05947-5
52. Wang B, Mao JH, Wang BY, Wang LX, Wen HY, Xu LJ, et al. Exosomal miR-1910-3p promotes proliferation, metastasis, and autophagy of breast cancer cells by targeting MTMR3 and activating the NF-κB signaling pathway. Cancer Lett. 2020;489:87–99. https://doi.org/10.1016/j.canlet.2020.05.038
53. Li Y, Jiang B, Zeng L, Tang Y, Qi X, Wan Z, et al. Adipocyte-derived exosomes promote the progression of triple-negative breast cancer through circCRIM1-dependent OGA activation. Environ Res. 2023;239(Pt 1):117266. https://doi.org/10.1016/j.envres.2023.117266
54. Lan M, Lei X, Lin Y, Mazur M, Ning J, Lee J, et al. Exosome circ_0076611-mediated macrophage M2 polarization to improve triple-negative breast cancer metastasis and the intervention of baicalin nano prodrugs. Colloids Surf B Biointerfaces. 2026;259:115333. https://doi.org/10.1016/j.colsurfb.2025.115333
55. Xun X, Hu H, Liu Q, Su R, Ai J. CAFs exosomal circFOXO1 promotes TNBC autophagy and radioresistance via miR-27a-3p/BNIP3 axis. Sci Rep. 2025;15(1):29273. https://doi.org/10.1038/s41598-025-13876-6
56. Razaviyan J, Sirati-Sabet M, Tafti A, Hadavi R, Karima S, Rajabibazl M, et al. Inhibition of miR-155 using exosomal delivery of antagomir can up-regulate PTEN in triple-negative breast cancer. Endocr Metab Immune Disord Drug Targets. 2024;24(14):1664–1676. https://doi.org/10.2174/0118715303289859240214103350
57. Wilson BE, Gorrini C, Cescon DW. Breast cancer immune microenvironment: from pre-clinical models to clinical therapies. Breast Cancer Res Treat. 2022;191(2):257–267. https://doi.org/10.1007/s10549-021-06431-0
58. Chen X, Song E. Turning foes to friends: targeting cancer-associated fibroblasts. Nat Rev Drug Discov. 2019;18(2):99–115. https://doi.org/10.1038/s41573-018-0004-1
59. Chen B, Sang Y, Song X, Zhang D, Wang L, Zhao W, et al. Exosomal miR-500a-5p derived from cancer-associated fibroblasts promotes breast cancer cell proliferation and metastasis through targeting USP28. Theranostics. 2021;11(8):3932–3947. https://doi.org/10.7150/thno.53412
60. Ye F, Liang Y, Wang J, Song J, Jin Y, Wang L, et al. A novel peptide MIB1-223aa encoded by exosomal circMIB1 from cancer-associated fibroblasts drives triple-negative breast cancer metastasis and stemness via stabilizing MIB1 to activate Notch signaling. J Adv Res. 2026;81:329–348. https://doi.org/10.1016/j.jare.2025.06.023
61. Sung JS, Kang CW, Kang S, Jang Y, Chae YC, Kim BG, et al. ITGB4-mediated metabolic reprogramming of cancer-associated fibroblasts. Oncogene. 2020;39(3):664–676. https://doi.org/10.1038/s41388-019-1014-0
62. Scognamiglio I, Cocca L, Puoti I, Palma F, Ingenito F, Quintavalle C, et al. Exosomal microRNAs synergistically trigger stromal fibroblasts in breast cancer. Mol Ther Nucleic Acids. 2022;28:17–31. https://doi.org/10.1016/j.omtn.2022.02.013
63. Qiao L, Dong C, Jia W, Sun G. RAB5A in triple-negative breast cancer: a critical role in macrophage reshaping in an exosomal miR-21-dependent manner. Endocr Relat Cancer. 2024;31(5):e230257. https://doi.org/10.1530/erc-23-0257
64. Shojaei S, Hashemi SM, Ghanbarian H, Sharifi K, Salehi M, Mohammadi-Yeganeh S. Delivery of miR-381-3p mimic by mesenchymal stem cell-derived exosomes inhibits triple-negative breast cancer aggressiveness: an in vitro study. Stem Cell Rev Rep. 2021;17(3):1027–1038. https://doi.org/10.1007/s12015-020-10089-4
65. Khazaei-Poul Y, Shojaei S, Koochaki A, Ghanbarian H, Mohammadi-Yeganeh S. Evaluating the influence of human umbilical cord mesenchymal stem cell-derived exosomes loaded with miR-3182 on metastatic performance of triple-negative breast cancer cells. Life Sci. 2021;286:120015. https://doi.org/10.1016/j.lfs.2021.120015
66. Farhadi S, Mohammadi-Yeganeh S, Kiani J, Hashemi SM, Koochaki A, Sharifi K, et al. Exosomal delivery of 7SK long non-coding RNA suppresses viability, proliferation, aggressiveness and tumorigenicity in triple-negative breast cancer cells. Life Sci. 2023;322:121646. https://doi.org/10.1016/j.lfs.2023.121646
67. Li W, Han G, Li F, Bu P, Hao Y, Huang L, et al. Cancer cell-derived exosomal miR-20a-5p inhibits CD8+ T-cell function and confers anti-programmed cell death 1 therapy resistance in triple-negative breast cancer. Cancer Sci. 2024;115(2):347–356. https://doi.org/10.1111/cas.16036
68. Wu Y, Han W, Dong H, Liu X, Su X. The rising roles of exosomes in the tumor microenvironment reprogramming and cancer immunotherapy. MedComm (2020). 2024;5(4):e541. https://doi.org/10.1002/mco2.541
69. Rocha KCE, Ying W, Olefsky JM. Exosome-mediated impact on systemic metabolism. Annu Rev Physiol. 2024;86:225–253. https://doi.org/10.1146/annurev-physiol-042222-024535
70. Yang L, Zhao S, Liu X, Zhang Y, Zhao S, Fang X, et al. Hypoxic cancer-associated fibroblast exosomal circSTAT3 drives triple-negative breast cancer stemness via miR-671-5p/NOTCH1 signaling. J Transl Med. 2025;23(1):814. https://doi.org/10.1186/s12967-025-06794-8
71. Li H, Fan J, Ma J, Qiao L, Sha T, Ma B. Exosomal miR-182-5p from breast cancer cells reprogram tumor-associated macrophages and promote triple-negative breast cancer progression by targeting Notch1 in macrophages. Arch Med Sci. 2025;21(4):1471–1486. https://doi.org/10.5114/aoms/187080
72. Hoshino A, Kim HS, Bojmar L, Gyan KE, Cioffi M, Hernandez J, et al. Extracellular vesicle and particle biomarkers define multiple human cancers. Cell. 2020;182(4):1044–1061.e18. https://doi.org/10.1016/j.cell.2020.07.009
73. Kim HI, Park J, Zhu Y, Wang X, Han Y, Zhang D, et al. Recent advances in extracellular vesicles for therapeutic cargo delivery. Exp Mol Med. 2024;56(4):836–849. https://doi.org/10.1038/s12276-024-01201-6
74. Torralba D, Baixauli F, Villarroya-Beltri C, Fernández-Delgado I, Latorre-Pellicer A, Acín-Pérez R, et al. Priming of dendritic cells by DNA-containing extracellular vesicles from activated T cells through antigen-driven contacts. Nat Commun. 2018;9(1):2658. https://doi.org/10.1038/s41467-018-05077-9
75. Salvador-Coloma C, Santaballa A, Sanmartín E, Calvo D, García A, Hervás D, et al. Immunosuppressive profiles in liquid biopsy at diagnosis predict response to neoadjuvant chemotherapy in triple-negative breast cancer. Eur J Cancer. 2020;139:119–134. https://doi.org/10.1016/j.ejca.2020.08.020
76. Wu H, Wang Q, Zhong H, Li L, Zhang Q, Huang Q, et al. Differentially expressed microRNAs in exosomes of patients with breast cancer revealed by next-generation sequencing. Oncol Rep. 2020;43(1):240–250. https://doi.org/10.3892/or.2019.7401
77. Di Modica M, Regondi V, Sandri M, Iorio MV, Zanetti A, Tagliabue E, et al. Breast cancer-secreted miR-939 downregulates VE-cadherin and destroys the barrier function of endothelial monolayers. Cancer Lett. 2017;384:94–100. https://doi.org/10.1016/j.canlet.2016.09.013
78. Koh MZ, Ho WY, Yeap SK, Mohd Ali N, Yong CY, Boo L, et al. Exosomal-microRNA transcriptome profiling of parental and CSC-like MDA-MB-231 cells in response to cisplatin treatment. Pathol Res Pract. 2022;233:153854. https://doi.org/10.1016/j.prp.2022.153854
79. Zhou Y, Yamamoto Y, Takeshita F, Yamamoto T, Xiao Z, Ochiya T. Delivery of miR-424-5p via extracellular vesicles promotes the apoptosis of MDA-MB-231 TNBC cells in the tumor microenvironment. Int J Mol Sci. 2021;22(2):844. https://doi.org/10.3390/ijms22020844
80. Gong C, Tian J, Wang Z, Gao Y, Wu X, Ding X, et al. Functional exosome-mediated co-delivery of doxorubicin and hydrophobically modified microRNA 159 for triple-negative breast cancer therapy. J Nanobiotechnology. 2019;17(1):93. https://doi.org/10.1186/s12951-019-0526-7
81. Yu S, Zhou Y, Niu L, Qiao Y, Yan Y. Mesenchymal stem cell-derived exosome miR-342-3p inhibits metastasis and chemo-resistance of breast cancer through regulating ID4. Genes Genomics. 2022;44(5):539–550. https://doi.org/10.1007/s13258-021-01200-1
82. Liu X, Zhang G, Yu T, Liu J, Chai X, Yin D, et al. CL4-modified exosomes deliver lncRNA DARS-AS1 siRNA to suppress triple-negative breast cancer progression and attenuate doxorubicin resistance by inhibiting autophagy. Int J Biol Macromol. 2023;250:126147. https://doi.org/10.1016/j.ijbiomac.2023.126147
83. Shao H, Im H, Castro CM, Breakefield X, Weissleder R, Lee H. New technologies for analysis of extracellular vesicles. Chem Rev. 2018;118(4):1917–1950. https://doi.org/10.1021/acs.chemrev.7b00534
84. Shi W, Jin X, Wang Y, Zhang Q, Yang L. High serum exosomal long non-coding RNA DANCR expression confers poor prognosis in patients with breast cancer. J Clin Lab Anal. 2022;36(3):e24186. https://doi.org/10.1002/jcla.24186
85. Qiu P, Guo Q, Lin J, Pan K, Chen J, Ding M. An exosome-related long non-coding RNAs risk model could predict survival outcomes in patients with breast cancer. Sci Rep. 2022;12(1):22322. https://doi.org/10.1038/s41598-022-26894-5
86. Yang Q, Cai X, Qian Y, Yang T, Xia W, Zhong M, et al. Implication of an exosome-based gene signature for estimating clinical outcomes of triple-negative breast cancer and assisting in individualized therapy. Sci Rep. 2025;15(1):37774. https://doi.org/10.1038/s41598-025-16751-6
87. Szymanowska A, Rodriguez-Aguayo C, Lopez-Berestein G, Amero P. Non-coding RNAs: foes or friends for targeting tumor microenvironment. Noncoding RNA. 2023;9(5):52. https://doi.org/10.3390/ncrna9050052
88. Youssef JR, Elgammal EM, Mahdy DM, Ghazi NF, Bebawy G. Recent progress in exosome-derived nanocarriers for breast cancer therapy: advances, translational barriers, and scale-up considerations. Pharm Res. 2026;43(6):1935–1977. https://doi.org/10.1007/s11095-026-04095-3
89. Yu M, Gai C, Li Z, Ding D, Zheng J, Zhang W, et al. Targeted exosome-encapsulated erastin induced ferroptosis in triple negative breast cancer cells. Cancer Sci. 2019;110(10):3173–3182. https://doi.org/10.1111/cas.14181
90. Yang P, Cao X, Cai H, Feng P, Chen X, Zhu Y, et al. The exosomes derived from CAR-T cell efficiently target mesothelin and reduce triple-negative breast cancer growth. Cell Immunol. 2021;360:104262. https://doi.org/10.1016/j.cellimm.2020.104262
91. Li K, Lin H, Liu A, Qiu C, Rao Z, Wang Z, et al. SOD1-high fibroblasts derived exosomal miR-3960 promotes cisplatin resistance in triple-negative breast cancer by suppressing BRSK2-mediated phosphorylation of PIMREG. Cancer Lett. 2024;590:216842. https://doi.org/10.1016/j.canlet.2024.216842
92. Théry C, Amigorena S, Raposo G, Clayton A. Isolation and characterization of exosomes from cell culture supernatants and biological fluids. Curr Protoc Cell Biol. 2006;Chapter 3:Unit 3.22. https://doi.org/10.1002/0471143030.cb0322s30
93. Gámez-Valero A, Monguió-Tortajada M, Carreras-Planella L, la Franquesa M, Beyer K, Borràs FE. Size-exclusion chromatography-based isolation minimally alters extracellular vesicles' characteristics compared to precipitating agents. Sci Rep. 2016;6:33641. https://doi.org/10.1038/srep33641
94. Busatto S, Vilanilam G, Ticer T, Lin WL, Dickson DW, Shapiro S, et al. Tangential flow filtration for highly efficient concentration of extracellular vesicles from large volumes of fluid. Cells. 2018;7(12):273. https://doi.org/10.3390/cells7120273
95. Gurunathan S, Kang MH, Jeyaraj M, Qasim M, Kim JH. Review of the isolation, characterization, biological function, and multifarious therapeutic approaches of exosomes. Cells. 2019;8(4):307. https://doi.org/10.3390/cells8040307
96. Lener T, Gimona M, Aigner L, Börger V, Buzás EI, Camussi G, et al. Applying extracellular vesicles based therapeutics in clinical trials - an ISEV position paper. J Extracell Vesicles. 2015;4:30087. https://doi.org/10.3402/jev.v4.30087
97. Pomatto MAC, Bussolati B, D’Antico S, Ghiotto S, Tetta C, Brizzi MF, et al. Improved loading of plasma-derived extracellular vesicles to encapsulate antitumor miRNAs. Mol Ther Methods Clin Dev. 2019;13:133–144. https://doi.org/10.1016/j.omtm.2019.01.001
98. Kooijmans SAA, Stremersch S, Braeckmans K, de Smedt SC, Hendrix A, Wood MJA, et al. Electroporation-induced siRNA precipitation obscures the efficiency of siRNA loading into extracellular vesicles. J Control Release. 2013;172(1):229–238. https://doi.org/10.1016/j.jconrel.2013.08.014
99. Rahgoshay M, Atashi A, Vaezi M, Ajorloo M, Amini-Kafiabad S, Ahmadvand M. Engineered exosomes: advanced nanocarriers for targeted therapy and drug delivery in hematological malignancies. Cancer Nanotechnol. 2025;16(1):33. https://doi.org/10.1186/s12645-025-00334-1
100. Li L, Wang S, Xue J, Lin Y, Su L, Xue C, et al. Development of spectral nano-flow cytometry for high-throughput multiparameter analysis of individual biological nanoparticles. Anal Chem. 2023;95(6):3423–3433. https://doi.org/10.1021/acs.analchem.2c05159
101. Lai CP, Mardini O, Ericsson M, Prabhakar S, Maguire C, Chen JW, et al. Dynamic biodistribution of extracellular vesicles in vivo using a multimodal imaging reporter. ACS Nano. 2014;8(1):483–494. https://doi.org/10.1021/nn404945r
102. Hindson BJ, Ness KD, Masquelier DA, Belgrader P, Heredia NJ, Makarewicz AJ, et al. High-throughput droplet digital PCR system for absolute quantitation of DNA copy number. Anal Chem. 2011;83(22):8604–8610. https://doi.org/10.1021/ac202028g
103. Gholizadeh S, Draz MS, Zarghooni M, Sanati-Nezhad A, Ghavami S, Shafiee H, et al. Microfluidic approaches for isolation, detection, and characterization of extracellular vesicles: current status and future directions. Biosens Bioelectron. 2017;91:588–605. https://doi.org/10.1016/j.bios.2016.12.062
104. Willms E, Cabañas C, Mäger I, Wood MJA, Vader P. Extracellular vesicle heterogeneity: subpopulations, isolation techniques, and diverse functions in cancer progression. Front Immunol. 2018;9:738. https://doi.org/10.3389/fimmu.2018.00738
105. Sork H, Corso G, Krjutskov K, Johansson HJ, Nordin JZ, Wiklander OPB, et al. Heterogeneity and interplay of the extracellular vesicle small RNA transcriptome and proteome. Sci Rep. 2018;8(1):10813. https://doi.org/10.1038/s41598-018-28485-9
106. Yang D, Jones MG, Naranjo S, Rideout WM 3rd, Min KHJ, Ho R, et al. Lineage tracing reveals the phylodynamics, plasticity, and paths of tumor evolution. Cell. 2022;185(11):1905–1923.e25. https://doi.org/10.1016/j.cell.2022.04.015
107. Luisotti L, Germelli L, Piccarducci R, Giacomelli C, Marchetti L, Martini C. Extracellular vesicles as vehicles for small non-coding RNA therapeutics: standardization challenges for clinical translation. Extracell Vesicles Circ Nucl Acids. 2025;6(3):403–432. https://doi.org/10.20517/evcna.2025.33
108. Duan H, Xu B, Luo P, Chen T, Zou J. Exosomal non-coding RNAs: orchestrators of intercellular crosstalk in the prostate cancer tumor microenvironment. Front Immunol. 2025;16:1644861. https://doi.org/10.3389/fimmu.2025.1644861
109. Meng W, Hao Y, He C, Li L, Zhu G. Exosome-orchestrated hypoxic tumor microenvironment. Mol Cancer. 2019;18(1):57. https://doi.org/10.1186/s12943-019-0982-6
110. Welsh JA, Goberdhan DCI, O'Driscoll L, Buzas EI, Blenkiron C, Bussolati B, et al. Minimal information for studies of extracellular vesicles (MISEV2023): from basic to advanced approaches. J Extracell Vesicles. 2024;13(2):e12404. https://doi.org/10.1002/jev2.12404
111. Parra A, Barranco I, Martínez-Díaz P, González E, Albóniga OE, Cabrera D, et al. Cryogenic electron microscopy reveals morphologically distinct subtypes of extracellular vesicles among porcine ejaculate fractions. Sci Rep. 2024;14(1):16175. https://doi.org/10.1038/s41598-024-67229-w
112. Baldasici O, Pileczki V, Cruceriu D, Gavrilas LI, Tudoran O, Balacescu L, et al. Breast cancer-delivered exosomal miRNA as liquid biopsy biomarkers for metastasis prediction: a focus on translational research with clinical applicability. Int J Mol Sci. 2022;23(16):9371. https://doi.org/10.3390/ijms23169371
113. Chen H, Yao H, Chi J, Li C, Liu Y, Yang J, et al. Engineered exosomes as drug and RNA co-delivery system: new hope for enhanced therapeutics? Front Bioeng Biotechnol. 2023;11:1254356. https://doi.org/10.3389/fbioe.2023.1254356
114. Tofolo MV, Berti FCB, Nunes-Souza E, Ruthes MO, Berti LF, Fonseca AS, et al. Non-coding RNAs as modulators of radioresponse in triple-negative breast cancer: a systematic review. J Biomed Sci. 2024;31(1):93. https://doi.org/10.1186/s12929-024-01081-y
115. O'Brien K, Breyne K, Ughetto S, Laurent LC, Breakefield XO. RNA delivery by extracellular vesicles in mammalian cells and its applications. Nat Rev Mol Cell Biol. 2020;21(10):585–606. https://doi.org/10.1038/s41580-020-0251-y
116. Jiang YZ, Ma D, Suo C, Shi J, Xue M, Hu X, et al. Genomic and transcriptomic landscape of triple-negative breast cancers: subtypes and treatment strategies. Cancer Cell. 2019;35(3):428–440.e5. https://doi.org/10.1016/j.ccell.2019.02.001
117. Lehmann BD, Bauer JA, Chen X, Sanders ME, Chakravarthy AB, Shyr Y, Pietenpol JA. Identification of human triple-negative breast cancer subtypes and preclinical models for selection of targeted therapies. J Clin Invest. 2011;121(7):2750–2767. https://doi.org/10.1172/JCI45014
118. Liu Y, Zhu XZ, Xiao Y, Wu SY, Zuo WJ, Yu Q, et al. Subtyping-based platform guides precision medicine for heavily pretreated metastatic triple-negative breast cancer: the FUTURE phase II umbrella clinical trial. Cell Res. 2023;33(5):389–402. https://doi.org/10.1038/s41422-023-00795-2
Declarations
Funding Statement
This work was supported by the National Natural Science Foundation of China (82273183, 82572981 to H.Z, 82472810 to H.D); Natural Science Foundation of Guangdong Province of China (2022A1515010925 to H.Z., 2021A1515011028 and 2022A1515011739 to H.D); the Major Project of the Open Joint Fund of the National Clinical Key Specialty Construction of Oncology, The First Affiliated Hospital of Henan University of Science and Technology (ZLKFJJ20230104 to H.Z); The Science Foundation of Guangdong Second Provincial General Hospital (PZ2024-001 to H.Z).
Competing Interest
The authors declare no financial or personal relationships with other individuals or organizations that could inappropriately influence or bias the content of this work. All authors have read the final version of the manuscript and confirm that there are no competing interests.
Consent for Publication
Consent for publication: All authors have approved the final version of the manuscript.
Use of Artificial Intelligence Disclosure
This article was written by human contributors. Artificial intelligence-based tools were used to improve grammar, language, and readability without affecting the article's scientific content, data interpretation, or conclusions. The authors reviewed and verified all content to ensure its accuracy and integrity.
Data Availability Statement
“No datasets were generated or analyzed in the current study.”
Ethics approval and consent to participate
Not applicable, as this study did not involve the conduct of research.
Authors’ affiliations
1. Institute of Precision Cancer Medicine and Pathology, School of Medicine, State Key Laboratory of Bioactive Molecules and Drugability Assessment, Jinan University, Guangzhou, China
2. Henan Key Laboratory of Cancer Epigenetics; Cancer Hospital, The First Affiliated Hospital, and College of Clinical Medicine of Henan University of Science and Technology, Luoyang, China
3. Department of Pathology, Gongli Hospital of Shanghai Pudong New Area, Shanghai, China
4. Department of Pathology, Heping Hospital, Changzhi Medical College, Changzhi, China
5. Department of Pharmacy, Red Cross Hospital, Jinan University, Guangzhou, China
6. Department of General Surgery, The First Affiliated Hospital of Jinan University, Guangzhou, China
7. Department of Breast Surgery, Nanchang People’s Hospital, Nanchang, China
8. Department of Radiotherapy, The Third Affiliated Hospital of Kunming Medical University, Yunnan Cancer Hospital, Peking University Cancer Hospital Yunnan, Kunming, China
9. Department of Pharmacy, Red Cross Hospital, Jinan University, MOE Key Laboratory of Tumor Molecular Biology, Jinan University, Guangzhou, China
CRediT authorship contribution statement
HC, RL, JM, WC, and HD: Writing - review & editing. HZ, RZ, WX, and HD: Conceptualization, Funding acquisition, Writing - review & editing. All authors contributed to the work and approved the final version of the manuscript.
ORCID ID
Hongmei Dong: https://orcid.org/0000-0003-4422-4172